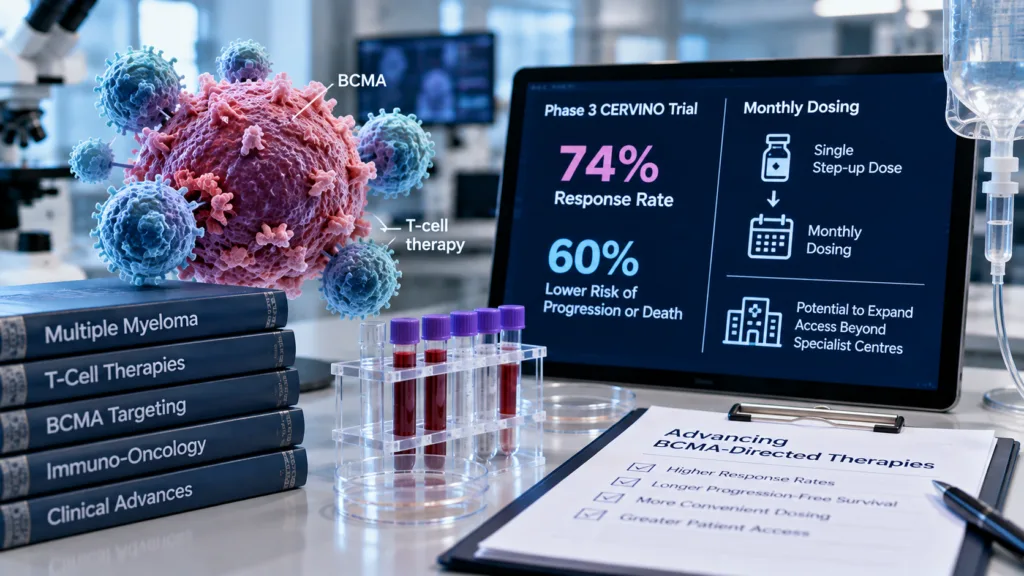
AbbVie has produced Phase 3 evidence suggesting that its investigational BCMA x CD3 bispecific antibody etentamig could become a significant new treatment for heavily pretreated multiple myeloma. In the CERVINO trial, 393 patients previously exposed to a proteasome inhibitor, immunomodulatory drug and anti-CD38 antibody were randomized between etentamig and investigator-selected standard therapies. Etentamig generated a 74% overall response rate compared with 45.7% for standard therapy and reduced the risk of disease progression or death by 60%, with a progression-free-survival hazard ratio of 0.40.
The survival trend was also encouraging at the first planned interim analysis. Twelve-month overall survival was 87.9% with etentamig compared with 72% for the control arm, although AbbVie said the prespecified statistical boundary for overall survival had not yet been crossed at the data cutoff. The independent monitoring committee nevertheless recommended unblinding the study because of the efficacy benefit.
Why does another BCMA therapy matter in an increasingly crowded myeloma market?
B-cell maturation antigen has become one of the most productive targets in multiple myeloma. CAR-T therapies and bispecific antibodies directed against BCMA can produce deep responses even after several previous treatment classes fail.
That success creates a new problem for drug developers: efficacy alone is no longer enough to differentiate a programme. Products increasingly compete on infection risk, cytokine release syndrome, neurotoxicity, dosing frequency, hospitalization requirements, manufacturing time and the ability to treat patients outside major academic centres.
Etentamig has been designed around that competitive reality. The molecule contains a low-affinity CD3-binding domain intended to temper T-cell activation, a high-avidity bivalent BCMA-binding domain and retained FcRn binding that supports less frequent dosing. AbbVie has not established that each structural feature independently causes the clinical profile seen in CERVINO, but the overall programme is explicitly intended to create a more practical treatment experience.
Why is monthly dosing potentially more important than it sounds?
Frequent visits can become a substantial burden for patients with relapsed multiple myeloma, many of whom are older, medically complex and already heavily treated. Some bispecific regimens require intensive dosing during treatment initiation and continued frequent administration afterward.
Etentamig uses one step-up dose followed by dosing once every four weeks from initiation. If that regimen receives regulatory approval without substantially different operational requirements, community oncology centres could theoretically manage treatment with fewer visits and less complex ramp-up than programmes requiring multiple step-up doses or ongoing weekly administration.
Convenience becomes commercially meaningful when efficacy is competitive. A drug that substantially underperforms will not win because it is easier to administer, but relatively similar clinical outcomes can shift physician preference toward the therapy that consumes fewer chair hours, requires less monitoring and imposes lower travel burdens.
What does the cytokine release syndrome profile suggest?
Cytokine release syndrome is a predictable consequence of strongly activating T cells and remains one of the defining management challenges for both bispecific antibodies and CAR-T therapy. Severe cases can produce hypotension, fever and organ dysfunction and may require hospitalization.
Among CERVINO patients receiving the single step-up regimen, cytokine release syndrome occurred in 28.3%, with 23.9% experiencing Grade 1 events and no Grade 3 or higher CRS reported. Only one patient experienced immune effector cell-associated neurotoxicity syndrome, or ICANS, and that event was Grade 1.
The infection data need more nuanced interpretation. Grade 3 or 4 infections occurred in 27.7% of etentamig patients compared with 19.2% receiving standard therapy, showing that clinically important infection risk remains. Fatal infections were numerically lower at 1.5% versus 3.1%, but those percentages alone should not be used to conclude superiority on infection mortality without fuller statistical analysis.
Can etentamig really move bispecific treatment into community oncology?
That will depend on more than the headline CRS rate. Community centres need clear management protocols, access to supportive care, rapid escalation pathways and confidence that early adverse reactions can be managed safely.
AbbVie argues that the dosing schedule and safety profile could support use across outpatient and community-based settings. That matters because many patients with multiple myeloma receive most of their care outside large transplant centres, yet advanced cellular and T-cell engaging therapies can be concentrated at specialist institutions.
Expanding treatment geography could enlarge the practical market without changing the biological eligibility population. A patient who is theoretically eligible for a therapy but cannot travel repeatedly to a major centre is not always a realistically addressable commercial patient.
How does a bispecific compare with CAR-T therapy?
CAR-T and bispecific antibodies both redirect T cells against cancer but solve different logistical problems. CAR-T therapy can produce deep and durable responses but requires collection and manufacturing of patient-specific cells, specialized treatment centres and management of substantial acute toxicities.
Bispecific antibodies are manufactured in advance and can be administered without individualized production. That makes treatment initiation potentially faster and allows broader distribution, although chronic dosing and infections create different burdens.
Etentamig therefore does not need to prove that CAR-T is ineffective. It needs to occupy the treatment circumstances in which physicians and patients prefer an immediately available therapy with predictable repeat dosing. The two modalities may increasingly become complementary rather than mutually exclusive.
Why are the CERVINO comparators important?
The control arm was not placebo. Investigators selected among established combinations including carfilzomib plus dexamethasone, elotuzumab plus pomalidomide and dexamethasone, or selinexor plus bortezomib and dexamethasone. That gives the observed 74% response rate and progression-free-survival benefit practical relevance in a population with few remaining conventional options.
The median patient had received three previous lines of therapy and had already been exposed to the three major treatment classes. This is therefore the type of clinical setting where physicians are actively searching for new mechanisms rather than simply rearranging familiar drug combinations.
Future trials will determine whether etentamig can move earlier. Earlier-line multiple myeloma increasingly involves combinations of highly effective therapies, and the efficacy threshold for inserting another T-cell engager becomes higher when patients have less refractory disease.
How important could etentamig become to AbbVie’s oncology strategy?
AbbVie remains best known commercially for its immunology and neuroscience franchises, while oncology has historically depended heavily on blood-cancer medicines such as Venclexta. Etentamig gives the company a potentially competitive position in one of hematology’s fastest-moving therapeutic classes.
AbbVie is also developing multiple modalities across cancer, including antibody-drug conjugates, multispecific antibodies, small molecules and CAR-T technologies. Etentamig could therefore serve both as a commercial product and as a combination platform if its dosing and safety prove manageable enough to pair with other agents.
The company plans to discuss CERVINO with global regulators, but etentamig remains investigational and has not yet been approved. Full Phase 3 presentation will provide further detail on depth of response, duration, measurable residual disease negativity and longer-term overall survival.
What data could change the competitive picture most?
Duration of response will be crucial. A high initial response rate creates excitement, but physicians need to know how long disease control lasts, especially when comparing a repeat-dose antibody with a one-time CAR-T procedure.
Long-term infection burden will also matter. BCMA-directed therapies can impair normal plasma cells and immunoglobulin production, creating chronic infection vulnerability. A monthly dosing schedule is commercially attractive only if ongoing immune suppression remains manageable.
Finally, real-world treatment location will become a key measure. If community oncologists genuinely adopt etentamig without routinely referring patients to tertiary centres, AbbVie could differentiate the product through accessibility rather than simply competing on laboratory measures.
CERVINO therefore suggests that the next phase of the myeloma competition may be less about proving that T-cell redirection works and more about making it practical. Etentamig’s 74% response rate establishes the efficacy argument. Its commercial fate may depend on whether one step-up dose and monthly administration are enough to turn sophisticated immunotherapy into something ordinary oncology practices can deliver routinely.