KalVista Pharmaceuticals, Inc., now a wholly owned company of Chiesi Group, announced on November 12, 2026, that five scientific presentations at the American College of Allergy, Asthma & Immunology Annual Scientific Meeting will examine real-world experiences and clinical outcomes associated with sebetralstat, marketed as EKTERLY. The research programme includes treatment satisfaction, reasons for switching therapies, longer-term quality of life and the healthcare burden associated with hereditary angioedema across different age groups.
The presentations reflect a significant change in the development and commercial trajectory of sebetralstat. The oral plasma kallikrein inhibitor is already approved in the United States and several international markets for treating acute hereditary angioedema attacks in adults and adolescents aged 12 years and older. Consequently, the focus is increasingly shifting from establishing efficacy under controlled trial conditions to understanding how treatment availability influences decisions, patient experience and healthcare utilisation in clinical practice.
The research also follows Chiesi Group’s completed acquisition of KalVista in June 2026, a transaction that brought sebetralstat into its global rare disease portfolio. Although the five presentations cover distinct research questions, they collectively address an important commercial and clinical issue: whether the convenience of oral on-demand therapy translates into better treatment experiences without compromising the established need for effective attack control. The November announcement outlines study designs and research objectives but does not provide complete numerical results for the newly scheduled presentations.
Why does real-world evidence matter after sebetralstat’s regulatory approval?
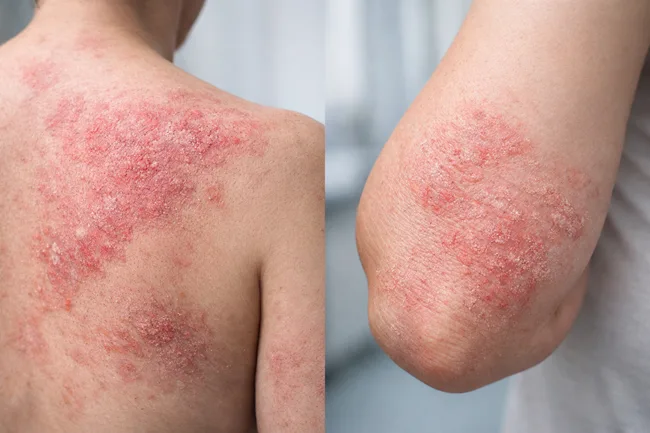
Hereditary angioedema is a rare condition involving recurrent episodes of tissue swelling that can affect the skin, gastrointestinal tract and upper airway. Attacks can be painful, unpredictable and disruptive, while swelling involving the airway can become life-threatening. Effective disease management therefore involves both appropriate prevention strategies and access to treatment for acute attacks.
Sebetralstat inhibits plasma kallikrein, an enzyme involved in the generation of bradykinin, a mediator associated with the swelling seen in certain forms of hereditary angioedema. By targeting this pathway, the medicine is intended to treat acute attacks after symptoms begin. It is not approved as a substitute for long-term prophylaxis or for the prevention of attacks.
The therapy’s regulatory development was supported by the Phase 3 KONFIDENT trial, which demonstrated faster onset of symptom relief with oral sebetralstat than with placebo. In the published study, median time to the beginning of symptom relief was 1.61 hours for the 300 mg dose, 1.79 hours for the 600 mg dose and 6.72 hours for placebo. The controlled trial provided evidence of treatment activity, while subsequent regulatory assessment established the authorised treatment regimen.
However, randomised trials cannot capture every consideration that shapes treatment in everyday life. Patients may experience attacks at inconvenient times, face challenges carrying or administering medication, or have different preferences concerning treatment routes. These factors can influence when treatment is used and how patients evaluate their disease management.
Real-world studies can provide information about such experiences after a medicine becomes available through routine prescribing. They may also reveal variation in treatment satisfaction, healthcare contact and patient behaviour that was not fully represented in registration trials. Nevertheless, observational evidence must be interpreted carefully because treatment selection and patient expectations can influence reported outcomes.
What will the EARLY study reveal about satisfaction with oral HAE attack treatment?
The EARLY study is an ongoing Phase 4 prospective observational investigation evaluating sebetralstat use in adolescents and adults with hereditary angioedema. One presentation scheduled for November 13 will examine treatment satisfaction using information collected from electronic attack diaries between January and June 2026. Participants were aged at least 12 years and had been prescribed or were already using sebetralstat for approximately three months before enrolment.
Patient satisfaction is a relevant outcome for an on-demand treatment because the practical burden of administering medication can influence the treatment experience. An oral medicine may be more convenient for some patients than a treatment requiring injection preparation or administration. However, convenience alone does not determine overall satisfaction, which also depends on symptom control, adverse effects, treatment availability and individual preferences.
Electronic diaries can provide useful information collected close to the time an attack occurs. They may reduce some of the recall limitations associated with asking patients to describe experiences weeks or months later. Nevertheless, completeness of diary entries and differences in patients’ willingness to record attacks can influence the resulting dataset.
The EARLY study’s observational design also creates important interpretive limitations. Patients were not randomly assigned to oral sebetralstat or an alternative therapy, and the treatment choices may reflect prior experiences or preferences. Those factors make it difficult to conclude that differences in satisfaction arise solely from the medicine itself.
The presentation may therefore be most useful for understanding whether patients report a favourable experience in routine use and which elements of treatment they value. It should not be presented as a controlled demonstration of superiority over injectable medicines or other approved HAE treatments.
Why are patients switching to sebetralstat from other hereditary angioedema treatments?
A second EARLY presentation will examine baseline reasons for switching to oral sebetralstat among 56 United States participants aged 12 years and older. The analysis focuses on individuals who had been prescribed or were using the medicine for on-demand HAE attack treatment before joining the study. It is intended to provide insight into the factors influencing patients’ treatment choices.
Treatment-route preferences are particularly relevant in hereditary angioedema because acute attacks can occur without warning. Patients using injectable medicines may need to carry equipment, prepare doses or administer treatment under circumstances that are physically or emotionally difficult. An oral option could reduce certain administration-related burdens for eligible patients, although individual suitability remains dependent on clinical considerations.
Understanding why patients switch is commercially important for Chiesi because it may help identify the practical features that influence sebetralstat adoption. A preference for oral administration could support demand, but switching decisions can also be affected by prior treatment experiences, access arrangements, physician recommendations and insurance coverage. These factors must be considered before treating the findings as evidence of a broad market preference.
The study is also subject to selection bias. Participants who have already switched to sebetralstat may be more likely to favour oral treatment than patients who remain satisfied with existing options. Their responses therefore cannot be assumed to represent the preferences of the entire hereditary angioedema population.
An additional limitation is that the presentation examines reasons for switching, not necessarily whether the new treatment produces better long-term clinical outcomes. Greater convenience could coexist with similar, better or worse experiences of attack control, depending on the individual patient and treatment characteristics. Direct comparative evidence would be required to establish relative clinical performance.
The commercial value of the EARLY findings will therefore depend on the quality and scope of the reported patient experience data. They may help Chiesi understand adoption behaviour, but they cannot independently establish that sebetralstat is clinically preferable to every injectable alternative.
How does KONFIDENT-S examine longer-term quality of life with sebetralstat?
KalVista’s third major research area concerns health-related quality of life during the KONFIDENT-S open-label extension study. The two-year programme evaluates participants who treat hereditary angioedema attacks with sebetralstat and includes periodic completion of the Angioedema Quality of Life questionnaire. The ACAAI presentation is scheduled for November 14.
Quality-of-life measurement is particularly relevant in a disorder characterised by unpredictable symptoms and anxiety concerning future attacks. Disease burden may extend beyond the physical consequences of individual swelling episodes to include work disruption, social limitations and concerns about accessing treatment. A medicine that supports effective attack management could influence some of these experiences.
However, changes in quality-of-life scores must be interpreted alongside the study design. KONFIDENT-S is open-label, meaning participants know they are receiving active treatment, and it does not provide the same concurrent control structure as the original randomised trial. Improvements over time may reflect treatment experience, changing disease activity, expectations or other influences.
The duration of follow-up offers a potential advantage because hereditary angioedema is a chronic condition requiring management over many years. Repeated assessments can help researchers understand whether reported quality-of-life changes persist, fluctuate or differ among participants. Yet longer observation alone does not establish causation, particularly when there is no untreated comparison group.
The results may complement the efficacy evidence from KONFIDENT by describing aspects of the treatment experience that conventional symptom-relief endpoints do not fully capture. The strongest interpretation will preserve the distinction between demonstrated clinical efficacy in controlled trials and supportive observational or open-label findings concerning patient experience.
What do the new studies reveal about the burden of HAE in children and adolescents?
Two additional ACAAI presentations address younger patients and their caregivers. One uses United States healthcare claims data to examine treatment patterns and resource utilisation among adolescents aged 12 to 17 years with hereditary angioedema. The other investigates the burden of injectable on-demand treatment among children aged 11 years and younger through a literature review and interviews with clinical experts.
The adolescent claims analysis covers the period from January 2021 through December 2024. This chronology is significant because it predates the United States approval and commercial launch of sebetralstat in 2025. Consequently, the findings describe the treatment and healthcare burden associated with existing care during the study period, rather than outcomes produced by sebetralstat use.
Claims databases can provide useful information about prescription activity, healthcare visits and recorded treatment utilisation. However, administrative claims do not always capture attack severity, treatment delays, reasons for clinical decisions or patient-reported outcomes. The resulting evidence is therefore more suitable for characterising healthcare patterns than for determining the effectiveness of individual therapies.
The separate study involving children aged 11 years and younger addresses an especially important treatment-access issue. Young children may depend on caregivers for recognition and management of attacks, while injectable administration can create additional practical and emotional challenges. Understanding those burdens can inform the development of future treatment options and more appropriate support systems.
However, the regulatory boundary remains clear. EKTERLY is currently authorised for acute hereditary angioedema attacks in patients aged 12 years and older, and its safety and efficacy have not been established for children younger than 12 under the United States label. Research concerning caregiver burden in younger children does not extend the medicine’s approved indication.
KalVista and Chiesi are continuing research into younger age groups, but any future expansion would require adequate clinical evidence and regulatory review. The present studies may help explain unmet needs, while the clinical development programme must establish whether treatment is suitable for those patients.
How could the Chiesi acquisition affect sebetralstat’s global commercial strategy?
Chiesi Group completed its acquisition of KalVista Pharmaceuticals on June 11, 2026, in a transaction valued at approximately $1.9 billion. The acquisition gave Chiesi ownership of sebetralstat and expanded its rare immunology business. KalVista’s shares ceased trading on Nasdaq following the transaction, meaning the company is no longer an independently listed biotechnology stock.
The acquisition also placed a newly commercialised hereditary angioedema treatment within an organisation with established rare disease operations and international infrastructure. Chiesi may be able to support broader market access, clinician engagement and continued evidence generation through its existing commercial capabilities. However, international approvals do not automatically establish equivalent reimbursement arrangements or product availability in every jurisdiction.
Sebetralstat achieved approximately $49 million in sales during 2025, according to information disclosed by Chiesi when it announced the acquisition. That figure provides an early commercial reference point following its United States launch in July 2025. Future growth will depend on prescribing adoption, eligible patient access, treatment frequency, regional launches and payer arrangements.
Real-world evidence can help support commercial execution by clarifying which treatment characteristics matter most to patients and clinicians. It may also provide information relevant to health technology assessments and discussions with payers. Nevertheless, favourable patient-reported findings are not a substitute for economic evidence demonstrating value under a specific reimbursement system.
The approved product’s safety profile and prescribing requirements also remain important. The United States label identifies headache as the most commonly reported adverse reaction and includes considerations involving drug interactions and hepatic impairment. Convenience of oral administration should not be interpreted as an absence of adverse effects or a reason to disregard individual treatment requirements.
What will determine the clinical value of KalVista’s new real-world research?
The five ACAAI presentations cover different aspects of hereditary angioedema care, and their evidentiary value will vary. The EARLY studies may provide insight into patient satisfaction and switching behaviour, while KONFIDENT-S can contribute longer-term observations concerning quality of life. The adolescent claims analysis and clinician interviews are better suited to characterising existing disease and treatment burdens.
These distinctions will be important when interpreting the complete results. Observational satisfaction data cannot establish comparative efficacy, and healthcare utilisation patterns recorded before a medicine’s launch cannot demonstrate its impact. Similarly, findings about children younger than 12 should not be confused with regulatory evidence supporting use in that population.
For Chiesi, the central opportunity is to move beyond proving that sebetralstat treats acute attacks and establish a more complete understanding of how it fits into everyday disease management. That evidence could support physician education, patient engagement and discussions about access, provided the limitations of each research method are respected.
The next meaningful test is whether these studies generate sufficiently detailed, reproducible findings to inform clinical practice and demonstrate practical value under routine treatment conditions. Sebetralstat already has an established regulatory indication supported by controlled clinical evidence. Its longer-term contribution to hereditary angioedema care will depend increasingly on treatment availability, appropriate use and the patient outcomes observed as clinical experience expands.