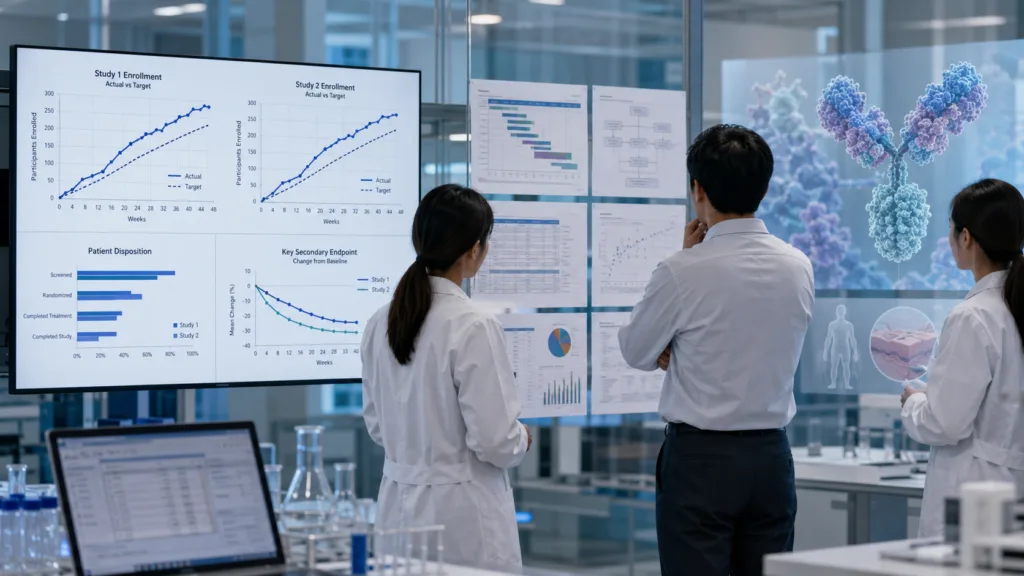
Zura Bio Limited has completed enrollment in the Phase 2 TibuSHIELD study of tibulizumab in hidradenitis suppurativa after randomising 247 participants, while its Phase 2 TibuSURE study in systemic sclerosis has already surpassed its target of 80 participants and is expected to finish recruitment in early July 2026. The biotechnology developer also plans to start another Phase 2 study of tibulizumab in a third immune-mediated disease before the end of 2026, creating a broader clinical program ahead of the first efficacy results.
The recruitment progress removes one of the immediate operational uncertainties surrounding the program, but it does not yet resolve the more important scientific question. Tibulizumab must demonstrate that simultaneously inhibiting interleukin-17A and B-cell activating factor can produce clinically meaningful benefits that exceed, or at least clearly differentiate the drug from, therapies targeting individual immune pathways.
Why exceeding enrollment targets improves execution confidence without reducing efficacy risk
Clinical trial recruitment can become a major bottleneck in diseases requiring tightly defined patient populations, particularly when several competing studies are drawing from the same specialist centres. Completing TibuSHIELD with more participants than originally planned therefore indicates that Zura Bio Limited and its clinical research partners were able to identify eligible adults with moderate to severe hidradenitis suppurativa without a prolonged delay.
The additional participants could improve the statistical stability of the analysis, reduce the influence of individual outliers and provide a somewhat larger safety dataset. This is particularly relevant for a dose-ranging study with two tibulizumab groups and a placebo arm, because the effective sample size available for each comparison remains considerably smaller than the headline enrollment figure.
However, over-enrollment should not be interpreted as evidence that tibulizumab is working. Recruitment performance demonstrates operational execution and interest in the study, not treatment efficacy. The value of the larger population will depend on whether it produces a consistent dose response, whether the key secondary endpoints support the primary analysis and whether discontinuations or missing data remain balanced across the treatment arms.
The systemic sclerosis enrollment milestone is also important because early diffuse cutaneous systemic sclerosis is uncommon, clinically heterogeneous and capable of affecting several organs. Recruiting beyond the target suggests that TibuSURE has accessed a sufficiently broad network of specialist centres. Yet a study containing slightly more than 80 participants will still have limited capacity to resolve smaller treatment effects or reliably examine numerous clinical subgroups.
Can dual IL-17A and BAFF inhibition deliver more than two familiar mechanisms combined?
Tibulizumab is a bispecific antibody designed to neutralise interleukin-17A and B-cell activating factor, commonly known as BAFF. Interleukin-17A contributes to inflammatory signalling, while BAFF supports B-cell survival and antibody-producing immune activity. The development hypothesis is that blocking both pathways could control diseases in which inflammatory, autoimmune and tissue-remodelling processes operate simultaneously.
That concept is more ambitious than conventional single-target biologic development. Instead of identifying one dominant cytokine and suppressing it, Zura Bio Limited is attempting to intervene in complementary components of immune dysfunction through a single molecule. This could potentially benefit patients whose disease remains active because blocking one pathway leaves another biologically relevant mechanism untouched.
The approach also creates a higher evidentiary burden. Tibulizumab must show that dual inhibition produces a meaningful clinical advantage rather than simply combining the biological effects and safety liabilities associated with two immune targets. A complex mechanism does not automatically create stronger efficacy, especially when disease activity is driven by additional pathways outside interleukin-17A and BAFF.
Early clinical exposure provides some reassurance but remains limited. Tibulizumab has previously been administered to 78 participants across three Phase 1b studies, including studies in rheumatoid arthritis and Sjögren’s syndrome. Those studies supported continued development and demonstrated pharmacological engagement of both targets, but they were not designed to establish efficacy in hidradenitis suppurativa or systemic sclerosis.
What must TibuSHIELD show in a hidradenitis suppurativa market with established biologics?
TibuSHIELD is a global, randomised, double-blind and placebo-controlled Phase 2 study assessing two doses of tibulizumab. The primary endpoint measures the percentage change from baseline in total abscess and inflammatory nodule count after 16 weeks. Secondary endpoints include HiSCR50 and HiSCR75, which evaluate whether participants achieve at least 50% or 75% reductions in abscess and nodule counts without worsening abscesses or draining fistulas.
Using percentage change as the primary endpoint may help detect treatment activity across a continuous spectrum rather than dividing participants into responders and non-responders. That can be valuable in an exploratory Phase 2 study focused on dose selection and signal detection. Nevertheless, categorical HiSCR responses are highly relevant to clinicians, regulators and comparisons with competing hidradenitis suppurativa programs.
Tibulizumab is entering a treatment landscape that already includes tumour necrosis factor inhibition through adalimumab and interleukin-17 pathway therapies such as secukinumab and bimekizumab. This means that demonstrating superiority to placebo will be necessary but may not be sufficient to establish meaningful commercial differentiation.
A competitive profile could emerge through deeper lesion reductions, stronger HiSCR75 responses, durability, performance among patients previously exposed to biologics or a more convenient maintenance schedule. Conversely, an improvement in average abscess and nodule count without convincing categorical responses could make the result scientifically interesting but commercially less decisive.
The first topline TibuSHIELD results expected in the fourth quarter of 2026 will therefore require careful interpretation beyond the primary endpoint. Dose separation, consistency between continuous and responder analyses, performance across prior-treatment groups and the balance between efficacy and adverse events will determine whether tibulizumab appears ready for a larger registration-oriented program.
Why TibuSURE may provide a more demanding test of tibulizumab’s biological thesis
Systemic sclerosis presents a substantially different challenge. The disease can involve skin thickening, vascular dysfunction, lung fibrosis, gastrointestinal complications and other organ manifestations. A therapy that affects one component may not necessarily alter the broader disease course, making endpoint selection and treatment duration particularly important.
TibuSURE is evaluating tibulizumab in adults with early diffuse cutaneous systemic sclerosis over a 24-week double-blind efficacy period. Its primary endpoint is the change in modified Rodnan Skin Score, a clinical assessment of skin thickness. Secondary evaluations include forced vital capacity and quantitative high-resolution computed tomography for interstitial lung disease, alongside measures of physical function and broader systemic response.
The modified Rodnan Skin Score is widely used in systemic sclerosis trials, but it is influenced by examiner technique, disease stage and the natural evolution of skin involvement. Research has suggested that an improvement of roughly five points may represent a clinically important difference for patients with diffuse cutaneous disease, although the relevance of a change also depends on baseline severity and treatment duration.
A 24-week assessment may provide an early efficacy signal, but systemic sclerosis can evolve slowly and inconsistently. A modest numerical skin improvement could therefore be difficult to interpret without evidence from lung, functional and composite endpoints. The relatively small study population further limits the ability to establish definitive effects across multiple organ systems.
The commercial opportunity would be meaningful if tibulizumab demonstrates coherent improvements in skin disease while also showing favourable trends in lung function or imaging. Existing approved therapies for systemic sclerosis-associated interstitial lung disease primarily focus on slowing pulmonary decline rather than broadly reversing systemic disease manifestations. A multi-domain benefit could therefore provide genuine differentiation, but the Phase 2 study may be better suited to identifying that possibility than proving it conclusively.
Does adding a third indication strengthen the platform or increase development risk too early?
Zura Bio Limited plans to disclose and begin a third Phase 2 tibulizumab indication before the end of 2026. This expansion signals confidence that interleukin-17A and BAFF biology may apply across several immune-mediated disorders rather than being limited to hidradenitis suppurativa and systemic sclerosis.
From a portfolio perspective, another indication could diversify clinical risk. A disappointing result in one disease would not necessarily invalidate the molecule if another condition depends more strongly on the targeted pathways. Conducting multiple studies can also generate comparative information about dosing, pharmacodynamics and patient selection.
The timing nevertheless introduces strategic risk because the new study is expected to start before Zura Bio Limited has reported efficacy data from either ongoing Phase 2 program. Launching another trial ahead of biological validation commits capital and management attention based primarily on mechanistic reasoning and early-stage evidence.
The quality of the third-indication decision will depend on the strength of human genetic, biomarker and clinical evidence connecting both interleukin-17A and BAFF to the selected disease. A broad commercial market alone would not justify expansion if the dual-target rationale is weak. The trial will also need to be sized and structured so that it does not compete excessively with preparations for potential pivotal hidradenitis suppurativa or systemic sclerosis studies.
Can Zura Bio finance broader development through the next major clinical decisions?
Zura Bio Limited reported cash and cash equivalents of approximately $225.6 million at the end of March 2026 and expects its resources to support planned operations through at least the end of 2028, including the third tibulizumab study. That runway is important because the clinical-stage developer must fund multiple Phase 2 trials while retaining the ability to prepare for larger studies if the results are positive.
Research and development expenditure is already rising as the tibulizumab program expands. Spending on the hidradenitis suppurativa study increased particularly sharply during the first quarter of 2026, reflecting the cost of global recruitment and clinical research organisation activity. A successful Phase 2 outcome would likely increase expenditure further because pivotal trials usually require substantially larger populations, longer follow-up and more extensive manufacturing commitments.
The biotechnology developer also holds tibulizumab under a licensing agreement with Eli Lilly and Company. Future development, regulatory and sales milestones, along with royalties on potential commercial sales, would affect the long-term economics of the program. These obligations do not prevent tibulizumab from becoming commercially attractive, but they reduce the proportion of future value retained by Zura Bio Limited and raise the capital required to progress the asset.
The existing cash position appears capable of carrying the program through its scheduled data catalysts. It does not remove financing risk if Zura Bio Limited attempts to advance several registration programs independently, particularly because the business does not generate product revenue. Positive Phase 2 data could create opportunities for additional financing or a development partnership, while ambiguous results could make capital significantly more expensive.
What will determine whether tibulizumab moves from an interesting mechanism to a viable therapy?
The upcoming data must establish more than statistical separation from placebo. TibuSHIELD needs to show that reductions in inflammatory lesions translate into convincing responder rates, that one dose provides a practical efficacy and safety balance and that results are not dependent on a narrow subgroup. TibuSURE needs to demonstrate that skin-score changes are clinically credible and supported by broader measures of organ function or disease activity.
Safety will also receive close scrutiny because tibulizumab simultaneously suppresses two immune pathways. The Phase 2 studies will need to characterise infections, treatment discontinuations, laboratory abnormalities and other immune-related adverse events across the tested doses. A stronger efficacy signal could support a somewhat more complex safety profile, but marginal efficacy would leave little tolerance for added risk.
Regulatory clarity will come only after the readouts. For hidradenitis suppurativa, Zura Bio Limited will need to determine which endpoints, duration and patient population can support pivotal development in a market where regulators already have experience reviewing several biologics. For systemic sclerosis, discussions are likely to focus on whether the observed effects are broad and durable enough to justify larger trials centred on skin disease, lung involvement or a composite disease measure.
The enrollment update therefore represents genuine operational progress rather than clinical validation. Zura Bio Limited has successfully positioned tibulizumab for two meaningful data readouts and expanded the program’s strategic possibilities. The fourth quarter of 2026 will begin revealing whether the dual-pathway thesis can translate into differentiated efficacy, while the systemic sclerosis results expected in the first half of 2027 may determine whether tibulizumab has the potential to become a broader autoimmune disease platform.