AstraZeneca’s Etcamah, or camizestrant, has produced two apparently conflicting Phase 3 outcomes that together may offer a more important lesson than either result viewed alone. On September 4, 2026, the United States Food and Drug Administration granted accelerated approval to camizestrant in combination with a CDK4/6 inhibitor for patients with HR-positive, HER2-negative advanced breast cancer whose tumours develop an ESR1 mutation while they remain on first-line aromatase inhibitor plus CDK4/6 therapy and before radiographic progression. In SERENA-6, that biomarker-directed strategy cut the risk of progression or death by 56% at the interim analysis, with median progression-free survival of 16.0 months versus 9.2 months for patients who continued standard therapy.
Only a week later, AstraZeneca reported that SERENA-4 had failed to achieve a statistically significant improvement in progression-free survival when camizestrant plus palbociclib was used broadly as upfront first-line treatment rather than selectively after an ESR1 mutation emerged. The numerical direction favoured camizestrant, but the study did not meet its primary objective. The contrast is striking because the same oral selective estrogen receptor degrader looks meaningfully effective when deployed against an emerging resistance mechanism yet failed to show statistically significant superiority when given to an unselected first-line population from the beginning.
Why does the difference between SERENA-6 and SERENA-4 matter so much?
HR-positive, HER2-negative breast cancer is biologically dependent on estrogen receptor signalling, making endocrine therapy a cornerstone of treatment. Aromatase inhibitors combined with CDK4/6 inhibitors have transformed first-line management, but resistance eventually develops in many patients. One important mechanism is mutation of ESR1, the gene encoding the estrogen receptor, which can allow tumour signalling to continue despite estrogen deprivation.
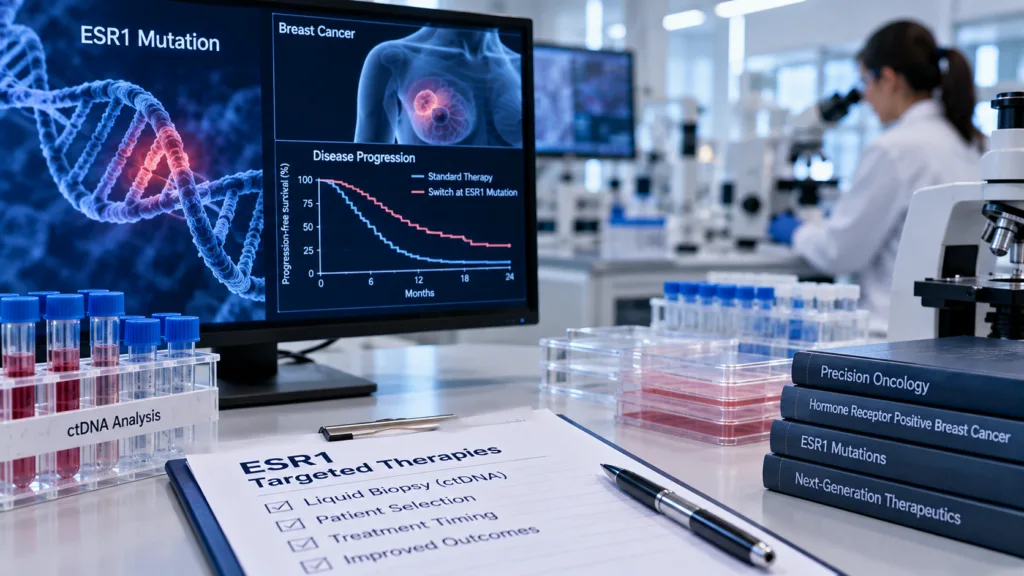
SERENA-6 was designed around that biological evolution rather than simply substituting one endocrine drug for another from day one. Patients started standard aromatase inhibitor plus CDK4/6 therapy, underwent serial circulating tumour DNA testing and switched to camizestrant only if an ESR1 mutation appeared before conventional imaging showed progression. Approximately 30% of patients with endocrine-sensitive HR-positive advanced breast cancer are estimated to develop ESR1 mutations during first-line therapy before clinical progression, creating a defined subgroup in which standard therapy may already be losing biological control even while scans still appear stable.
That makes SERENA-6 more than a drug trial. It is also a trial of treatment timing. The strategy assumes that molecular progression begins before radiographic progression and that intervening during that window may preserve disease control better than waiting until tumours visibly enlarge.
What did ctDNA monitoring reveal that imaging had not yet shown?
Circulating tumour DNA provides fragments of cancer-derived DNA released into the bloodstream. When an ESR1 mutation appears during aromatase inhibitor treatment, clinicians may be observing the molecular emergence of endocrine resistance before enough resistant tumour cells accumulate to produce radiographic progression.
Updated SERENA-6 data strengthened that interpretation. AstraZeneca reported median progression-free survival of 16.8 months with camizestrant plus a CDK4/6 inhibitor compared with 9.2 months for patients continuing an aromatase inhibitor combination, representing a 55% reduction in the risk of progression or death at the later analysis. Median second progression-free survival also improved to 25.7 months from 19.1 months, suggesting the early switch did not merely move progression forward into a subsequent line of therapy without creating longer-term value.
The molecular response was particularly notable. Total circulating tumour DNA declined by a median 99% after eight weeks in patients who switched to camizestrant, compared with a 64% increase among those remaining on standard treatment. Approximately 51% of evaluable patients in the camizestrant arm achieved complete ctDNA clearance compared with just 1.9% in the control group.
Those findings suggest that changing therapy when the resistant clone becomes detectable can suppress emerging disease before conventional criteria declare treatment failure. If replicated across other cancers and resistance pathways, the concept could turn liquid biopsy from a tool used primarily for selecting initial therapy into an active surveillance system that determines when treatment should change.
Why might camizestrant fail when given to everyone from the start?
A drug designed to overcome a particular resistance mechanism does not necessarily provide enough additional benefit when that resistance mechanism is absent. Patients entering SERENA-4 had not received systemic therapy for advanced disease and were not selected because an ESR1 mutation had emerged. Many may therefore remain highly sensitive to conventional aromatase inhibition.
Replacing the aromatase inhibitor immediately with camizestrant exposes every patient to the newer drug, including those for whom standard endocrine therapy could have remained effective for a long period. The incremental benefit across such a heterogeneous population may consequently be diluted. AstraZeneca reported a numerical improvement in progression-free survival in SERENA-4 but not the statistically significant improvement required for the trial to meet its primary endpoint.
This distinction is commercially relevant because pharmaceutical companies generally prefer broad first-line labels. Large eligible populations produce greater revenue opportunities and simpler treatment pathways than biomarker-triggered switching strategies that require serial testing. SERENA-4 suggests that the narrower precision-treatment model may nevertheless be the clinically stronger use of camizestrant.
Does this make Etcamah a companion-diagnostics story as much as a drug story?
The FDA approval explicitly depends on detecting ESR1 mutation through an FDA-authorized test. That makes regular molecular monitoring an operational requirement rather than an optional research exercise. The agency simultaneously approved Guardant360 CDx as a companion diagnostic for identifying eligible ESR1-mutated patients.
Hospitals and oncology practices therefore need to determine when to test, how frequently to repeat testing and how rapidly clinicians can act once a mutation appears. A patient could theoretically develop an ESR1 mutation months before a scheduled scan shows progression, meaning the value of Etcamah may depend heavily on whether real-world practices implement the surveillance strategy used in SERENA-6.
This creates a potentially important commercial opportunity for liquid-biopsy companies. If molecular progression becomes an actionable treatment trigger rather than simply a prognostic observation, recurring ctDNA testing could become embedded into chronic management of metastatic cancer. The economic ecosystem would then include the drug, the diagnostic assay, laboratory infrastructure and clinical decision rules determining when a positive result justifies changing therapy.
Why was the FDA decision notable despite earlier regulatory uncertainty?
The Etcamah programme had faced a more complicated regulatory path than the final approval headline suggests. In April 2026, an FDA advisory committee did not reach a majority vote supporting the clinical benefit of switching to camizestrant upon ESR1 mutation detection before radiographic progression. The agency later extended its review to assess additional data.
The eventual accelerated approval indicates that the FDA concluded the available evidence was sufficient to make the therapy available while confirmatory evidence continues. The agency requires AstraZeneca to complete ongoing studies including SERENA-6 follow-up and additional randomized work examining the clinical benefit of switching therapy before visible progression.
That regulatory history highlights the novelty of the treatment paradigm. Regulators are not simply assessing whether one drug produces a better response than another after documented progression. They are evaluating whether acting on molecular evidence of future treatment failure creates enough clinical benefit to justify changing therapy earlier.
What does the SERENA-4 failure mean for AstraZeneca commercially?
The failed primary endpoint reduces the likelihood that Etcamah will quickly replace aromatase inhibitors across the entire first-line HR-positive advanced breast cancer population. That closes, or at least delays, the broadest possible commercial route.
The approved biomarker-directed population can still be substantial. HR-positive, HER2-negative disease accounts for most breast cancers, and ESR1 mutations become increasingly common under endocrine selection pressure. AstraZeneca therefore retains an opportunity to establish Etcamah during first-line treatment, but its success will depend on building a new treatment behaviour around serial molecular testing rather than competing simply for initial prescriptions.
The strategy may also create an advantage if physicians become comfortable with Etcamah before progression. Once a patient switches successfully based on ctDNA, continued clinical benefit can establish familiarity that influences later treatment decisions.
Could this trial design become more important than the drug itself?
Cancer treatment traditionally changes when physicians can see evidence that the current therapy has stopped working. Imaging reveals tumour growth, symptoms worsen or laboratory abnormalities emerge. Molecular monitoring raises the possibility of intervening before any of those developments occur.
SERENA-6 provides unusually strong Phase 3 evidence supporting that strategy in a defined setting. Patients were not treated because their cancer had already progressed by conventional criteria; they were treated because a molecular marker indicated that resistance was developing. The subsequent improvement in progression-free survival suggests that waiting for radiographic confirmation may sacrifice a therapeutic window.
That does not mean every newly detected resistance mutation should trigger treatment. Serial testing creates false-positive risk, biological complexity and cost, and different mutations may not have therapies capable of exploiting early detection. The value of the model depends on having both a reliable marker and an effective intervention targeted to the resistance mechanism.
AstraZeneca’s seemingly contradictory Phase 3 outcomes therefore fit together better than they initially appear. SERENA-4 says camizestrant is not necessarily superior enough to replace standard endocrine therapy for everyone from the start. SERENA-6 says it can be highly valuable when biology shows that standard therapy is beginning to fail. That may prove to be a more significant lesson for precision oncology than a simple first-line drug victory.