The United States Food and Drug Administration has cleared University of Colorado Anschutz Medical Campus investigators to begin clinical testing of an experimental chimeric antigen receptor T-cell therapy designed for adults with advanced colorectal cancer and pediatric patients with refractory solid tumors. The investigational cells recognize B7-H3 on tumor cells while carrying an additional homing mechanism intended to help them migrate toward tumors producing the inflammatory chemokine interleukin-8.
The first clinical study is expected to begin in December 2026 and will initially focus on whether the engineered cells can be administered safely and demonstrate evidence of reaching and attacking solid tumors. The therapy will be manufactured at the Gates Biomanufacturing Facility on the University of Colorado Anschutz Medical Campus, giving the academic program control over a technically demanding personalized manufacturing process.
FDA clearance permits the investigators to conduct the clinical study. It does not mean the CAR T-cell product has been approved for colorectal cancer or any other solid tumor, and the preclinical findings supporting the approach should not be interpreted as evidence that it will produce tumor responses in patients.
That distinction matters because solid tumors remain one of the largest unresolved challenges for CAR T-cell therapy. The technology has transformed treatment of several hematological malignancies, yet reproducing that success in colorectal cancer and other solid cancers requires engineered cells to overcome physical barriers, hostile tumor biology and inconsistent target expression after they are infused.
Why do CAR T cells face a much tougher biological problem in solid tumors than in blood cancers?
CAR T-cell therapies work by collecting a patient’s T cells, genetically modifying them to recognize a selected surface antigen and returning the engineered cells to the patient. The therapeutic logic is powerful when malignant cells consistently express a target that can be reached easily by circulating immune cells, as occurs with several B-cell malignancies.
A solid tumor creates a different environment. Engineered T cells first have to leave the bloodstream, migrate through tissue, penetrate the tumor architecture and survive long enough inside a metabolically and immunologically hostile microenvironment to destroy cancer cells. Dense stromal tissue, abnormal vasculature, suppressive immune cells and inhibitory signaling can all reduce effectiveness.
Tumor heterogeneity creates another problem. If only a subset of cancer cells expresses the chosen antigen strongly enough, CAR T cells may eliminate those cells while antigen-negative populations survive. Pressure from treatment can potentially select for cancer cells that reduce or lose expression of the target, allowing the tumor to continue growing.
Colorectal cancer illustrates these challenges particularly well because it is common, biologically heterogeneous and usually treated with surgery, chemotherapy, targeted drugs and immunotherapy according to disease stage and molecular profile. Cellular therapies would generally be considered experimentally in advanced disease after established options have been exhausted rather than replacing those treatments based on an early clinical trial.
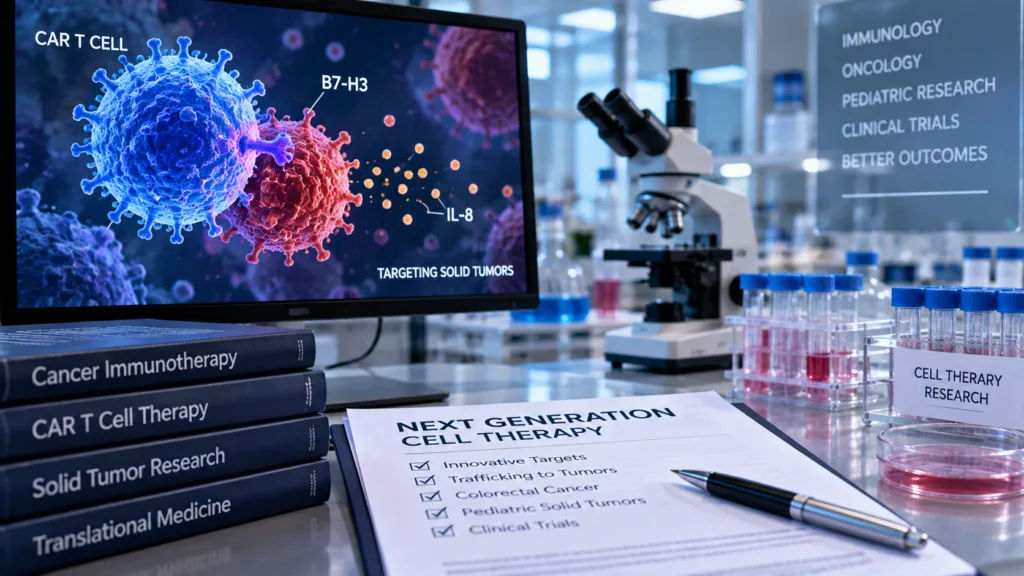
The CU Anschutz program is therefore trying to solve two problems simultaneously. B7-H3 provides the tumor-recognition target, while the CXCR2 component is intended to help the engineered cells physically reach areas of tumor tissue producing IL-8.
How does the B7-H3 and CXCR2 design attempt to improve CAR T-cell trafficking?
B7-H3 is an immune-regulatory protein that is expressed across several solid tumor types and has attracted growing interest as a therapeutic target. The University of Colorado investigators identified it as appealing partly because B7-H3 is present in a substantial proportion of colorectal cancers and in several pediatric solid tumors, potentially allowing one basic CAR construct to be investigated across more than one malignancy.
The second engineering component addresses trafficking rather than direct tumor recognition. Many solid tumors produce IL-8, a chemokine involved in inflammation and the recruitment of certain immune-cell populations. The Colorado researchers engineered their B7-H3 CAR T cells to express CXCR2, a receptor responsive to IL-8 signals.
The intended effect is analogous to giving the CAR T cells an additional navigation system. Instead of relying only on natural T-cell migration to place sufficient numbers of therapeutic cells inside the tumor, CXCR2 could allow the cells to follow an IL-8 concentration gradient toward cancer tissue.
Earlier laboratory research from the group demonstrated that B7-H3-directed CAR T cells engineered with CXCR2 showed enhanced migration toward IL-8 and stronger antitumor effects in experimental models of pediatric sarcoma. Related research in canine osteosarcoma has also been used to investigate whether the dual design improves cellular trafficking and activity in spontaneous solid tumors.
Those findings provide a mechanistic rationale for human testing, but animal models and laboratory systems do not recreate all the barriers present in advanced human colorectal cancer. Tumor size, prior treatment, antigen heterogeneity and immune suppression may all influence whether sufficient CAR T cells can reach malignant tissue after infusion.
Why is B7-H3 potentially attractive across colorectal cancer and pediatric solid tumors?
The search for appropriate antigens has slowed solid-tumor CAR T development because ideal targets are uncommon. A useful target needs to be expressed strongly enough on cancer cells to permit recognition while being sufficiently limited on essential normal tissues to reduce the risk of destructive off-tumor immune activity.
B7-H3 is being investigated by multiple drug developers because expression has been reported in a range of cancers, including colorectal tumors, sarcomas and several pediatric malignancies. Its distribution provides the possibility of creating therapies that are not limited to one rare molecular mutation or one highly restricted cancer subtype.
Broad expression does not automatically establish therapeutic safety. CAR T cells are living medicines capable of expanding after administration, so even relatively low antigen expression on normal tissues can become important if the engineered immune cells recognize those tissues. Early clinical dose escalation will consequently need to characterize toxicities carefully before the investigators can meaningfully assess antitumor activity.
Target density may also influence response. Tumors with high B7-H3 expression could theoretically be easier for the engineered cells to recognize than tumors with heterogeneous or low-level expression. Clinical development may eventually require a validated method for measuring expression and determining whether patient selection improves the likelihood of benefit.
The initial trial should therefore begin to answer not only whether the cells can be given safely but whether B7-H3 biology in actual patient tumors resembles the preclinical assumptions underlying the program.
What safety questions will matter when the first patients receive the experimental CAR T therapy?
CAR T-cell treatment can produce serious immune-related toxicities, including cytokine release syndrome and neurological complications, although risk varies substantially according to the CAR construct, target, dose and disease. A new first-in-human solid-tumor design adds uncertainty because neither the B7-H3 targeting component nor the CXCR2 trafficking strategy has yet been established clinically in this specific configuration.
Enhancing tumor homing is potentially beneficial, but it creates a logical safety question as well. If CXCR2 increases migration of engineered cells toward inflammatory signals outside the tumor, investigators will need to understand whether the cells accumulate in unintended tissues or create inflammatory toxicity.
On-target, off-tumor recognition is another major consideration. B7-H3 expression in normal tissues must be sufficiently limited or biologically inaccessible to prevent clinically important damage when large numbers of activated T cells encounter the target.
The clinical team will also monitor more conventional cellular-therapy risks associated with lymphodepleting treatment, infection, cytopenias and manufacturing variability. Patients entering an early cell-therapy trial are often heavily pretreated, making attribution of adverse events particularly complicated.
This is why FDA clearance to start the study should not be interpreted as an endorsement of efficacy. The initial cohorts are designed to establish whether the proposed dose and cellular design are tolerable enough to justify further testing.
Why does on-campus manufacturing matter for an academic CAR T program?
CAR T-cell therapy is not manufactured like a conventional vial of medicine. Patient cells must be collected, genetically modified, expanded under controlled conditions, tested for identity, potency and contamination, and released before administration. Every manufacturing delay can matter for a patient with progressive advanced cancer.
The Gates Biomanufacturing Facility gives CU Anschutz researchers the capability to manufacture the experimental cells within the same academic ecosystem housing the cancer center, university research laboratories, Children’s Hospital Colorado and UCHealth University of Colorado Hospital. That proximity can reduce some of the coordination barriers between discovery science, manufacturing and clinical investigation.
Academic manufacturing can also allow investigators to test concepts that may initially be too early or commercially uncertain for a large pharmaceutical company. Philanthropic support has helped the Colorado program progress from laboratory development toward clinical testing, illustrating how institutional infrastructure can bridge the gap between promising translational research and a first-in-human study.
Scale becomes a different problem if the therapy eventually succeeds. A manufacturing process capable of supplying a small academic trial would need to become much more standardized, robust and economically sustainable before broad multicenter development or commercialization.
Manufacturability could therefore become an important secondary test of the program. A highly effective cellular therapy that takes too long to produce, fails frequently during manufacturing or requires exceptionally costly infrastructure can still struggle to reach patients.
Could this approach eventually extend beyond colorectal cancer?
The underlying strategy may have relevance to other malignancies in which B7-H3 is expressed and IL-8 contributes to the tumor microenvironment. CU Anschutz investigators have identified pediatric solid tumors as an early clinical population, while laboratory research has examined sarcomas and other cancer models.
B7-H3 is also being investigated in breast, lung, ovarian and other tumors, creating theoretical opportunities for broader development if the initial clinical study establishes an acceptable safety profile and evidence of biological activity. Each cancer would nevertheless require appropriate clinical evidence rather than extrapolation from colorectal cancer.
IL-8 biology may likewise vary substantially among tumors. The CXCR2 homing approach is most likely to matter when tumors produce enough relevant chemokine signal to attract the engineered cells, making biomarker studies potentially important as the program develops.
Other developers are pursuing different ways of overcoming solid-tumor CAR T limitations, including regional administration, armored CAR T cells, multi-antigen constructs and combinations intended to alter the tumor microenvironment. The Colorado approach is therefore one of several competing strategies rather than an established solution to the solid-tumor problem.
Its advantage is mechanistic clarity: one component is intended to recognize the tumor and another to improve the probability that therapeutic cells reach it. The clinical study will determine whether that elegant design remains useful after the complexity of human cancer is introduced.
What would constitute an encouraging result from the first clinical study?
For an early cellular-therapy trial, success does not require proving that the treatment extends survival. The first milestone is establishing that manufacturing is feasible, patients can receive the cells and serious toxicities remain manageable across planned doses.
Evidence that engineered cells expand, persist and traffic into tumor tissue would strengthen the biological case even before objective responses are fully characterized. Tumor biopsies and circulating biomarkers could potentially help investigators determine whether the CXCR2 modification is performing the function intended by the preclinical research.
Objective tumor regression would obviously attract attention, particularly in heavily pretreated patients, but small uncontrolled cohorts require cautious interpretation. Isolated responses can justify continued development without establishing efficacy across a wider population.
Durability will become increasingly important if responses appear. Solid tumors can recur after antigen loss or immune escape, so investigators will need to determine whether B7-H3 targeting provides sustained pressure on the disease.
The FDA clearance therefore moves an inventive CAR T architecture across a critical boundary, from animal and laboratory experiments into human testing. CU Anschutz researchers have designed the cells to recognize a widely expressed tumor antigen and follow an inflammatory signal toward cancer tissue, addressing two barriers that have repeatedly undermined solid-tumor CAR T programs. The December trial start will begin revealing whether those engineering advantages translate into tolerable cellular behavior in patients, which must be established before any discussion of clinical efficacy becomes convincing.