Lundbeck has received United States Food and Drug Administration Orphan Drug Designation for asedebart, or Lu AG13909, its investigational monoclonal antibody targeting adrenocorticotropic hormone for the treatment of endogenous Cushing’s syndrome. The designation adds regulatory momentum to a program already in Phase 2 proof-of-concept development and gives Lundbeck a potential route into a rare endocrine disorder characterized by chronic cortisol excess and substantial cardiovascular, metabolic and neuropsychiatric morbidity.
The development should not be confused with an approval or even evidence that asedebart will ultimately provide sufficient clinical benefit to support registration. FDA Orphan Drug Designation can provide development incentives for therapies targeting rare diseases, including potential fee exemptions, tax-related incentives and, if a medicine is eventually approved for the designated indication, a period of orphan market exclusivity. The designation does not establish efficacy, safety or a favorable benefit-risk profile.
What makes asedebart scientifically interesting is where it intervenes in the disease pathway. Several existing medical approaches to Cushing’s syndrome attempt to suppress cortisol synthesis, block cortisol action or influence the pituitary tumor responsible for excess ACTH secretion. Asedebart instead binds ACTH itself, potentially interrupting the hormonal signal that tells the adrenal glands to produce cortisol and other steroids.
Why does neutralizing ACTH create a different treatment strategy for Cushing’s disease?
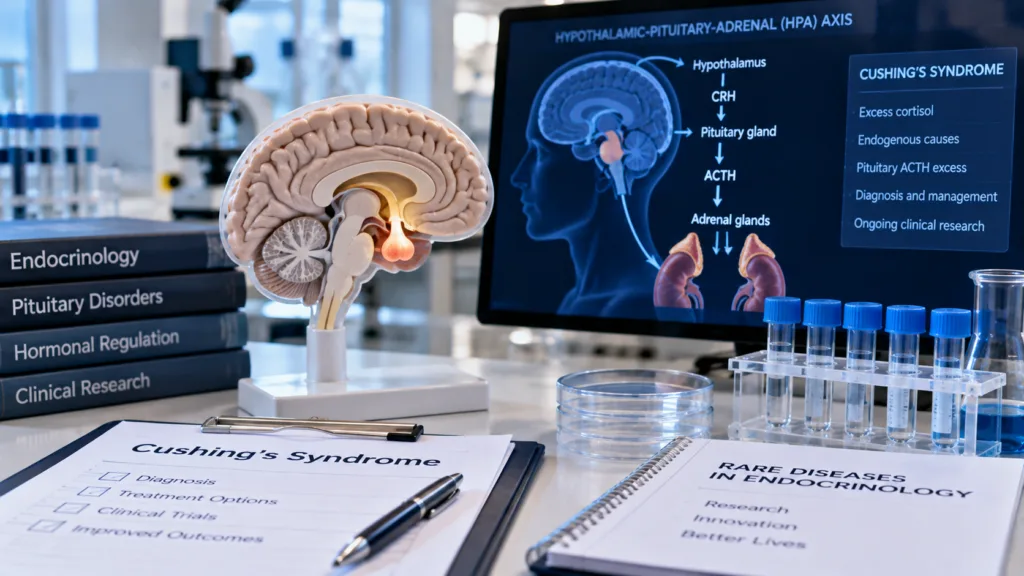
Cushing’s syndrome describes the clinical consequences of prolonged excessive exposure to cortisol. Endogenous disease can arise through several mechanisms, but in ACTH-dependent Cushing’s syndrome the adrenal glands are being persistently stimulated by excessive ACTH. The most common ACTH-dependent form is Cushing’s disease, in which a pituitary adenoma produces too much ACTH.
That hormone drives the adrenal cortex to produce glucocorticoids, mineralocorticoids and androgens. Excessive cortisol in particular can contribute to hypertension, diabetes, abnormal fat distribution, muscle weakness, osteoporosis, infection risk, mood disturbance and cardiovascular complications. Effective treatment therefore depends not simply on reducing one laboratory measurement but on achieving durable normalization of the hormonal environment without replacing one endocrine problem with another.
Asedebart is a humanized monoclonal antibody designed to bind ACTH with high affinity and prevent the hormone from activating melanocortin 2 receptors in the adrenal gland. Blocking that receptor interaction should reduce downstream steroid production, potentially allowing clinicians to control cortisol excess without directly inhibiting individual steroidogenic enzymes.
The concept is attractive because ACTH sits upstream of several adrenal hormones. However, an upstream target can also create complex physiological effects. ACTH forms part of the hypothalamic-pituitary-adrenal axis, a tightly regulated system essential to the body’s stress response, blood pressure regulation and metabolic homeostasis. Excessive suppression could therefore create clinically important consequences if cortisol production falls below the desired range.
Dose titration will consequently be central to development. The objective is not to eliminate cortisol but to bring pathological secretion toward physiological levels and keep it there consistently.
What does the ongoing Phase 2 BalanCeD study tell us about asedebart so far?
Lundbeck is evaluating asedebart in the Phase 2 BalanCeD study, a multisite, open-label dose-titration trial in adults with Cushing’s disease. The study is designed to examine safety, tolerability, pharmacokinetics and the drug’s effect on cortisol production, including urinary free cortisol, an established biochemical measure used in the assessment of hypercortisolism.
Preliminary Part A data presented at ENDO 2026 indicated that urinary free cortisol normalized in most evaluable participants who completed individualized intravenous dose titration. That provides early evidence that blocking ACTH can produce the expected downstream pharmacodynamic effect in human disease rather than only in laboratory models.
The data remain preliminary. An open-label dose-titration study lacks a randomized placebo-controlled comparator, making it difficult to separate drug effect from natural biological variability or other influences on cortisol measurements. Cushing’s disease can show substantial day-to-day hormonal fluctuation, which makes repeated assessment particularly important.
The number of patients contributing to the early analysis was also limited, and successful biochemical normalization does not automatically establish meaningful clinical improvement. Future datasets will need to show whether cortisol control is maintained, whether symptoms and disease-related comorbidities improve, and what happens when patients transition between intravenous and subcutaneous administration.
Safety will be equally important. A therapy that reliably reduces cortisol could create adrenal insufficiency if the pharmacological effect is too strong or difficult to titrate. Investigators will need to understand how rapidly ACTH blockade can be adjusted, how predictable the dose-response relationship is and whether prolonged antibody exposure creates additional immune or endocrine effects.
How could asedebart fit against surgery and existing medicines for Cushing’s disease?
Surgery remains the preferred first-line intervention for many patients with pituitary Cushing’s disease when the responsible tumor can be identified and removed safely. Successful transsphenoidal surgery can produce remission by removing the source of excess ACTH, but not every patient is a surgical candidate and disease can persist or recur after an initial procedure.
Medical therapy becomes particularly important for patients with persistent disease, recurrent disease, delayed surgical benefit or situations where surgery is not feasible. Current approaches include drugs that inhibit adrenal steroid synthesis, medicines acting at the pituitary level and treatments that block glucocorticoid receptors.
Each strategy has limitations. Steroidogenesis inhibitors can effectively reduce cortisol but may require frequent biochemical monitoring and can influence other adrenal steroids. Pituitary-directed therapies may not control disease in every patient, while glucocorticoid receptor blockade can improve clinical consequences of cortisol excess without making serum cortisol a straightforward marker of treatment response.
An ACTH-neutralizing antibody could occupy a different position. By targeting the hormonal driver before it reaches the adrenal gland, asedebart may allow a more direct suppression of ACTH-dependent steroid production without requiring inhibition of individual enzymes.
Whether that theoretical advantage becomes clinically meaningful will depend on control, predictability and tolerability. A medicine that works upstream but produces difficult-to-manage hormonal suppression may not offer a practical improvement over established therapies. Conversely, consistent cortisol normalization with convenient subcutaneous dosing could create a differentiated option.
Why is the orphan designation broader than the current Cushing’s disease trial?
The FDA designation covers endogenous Cushing’s syndrome, while the BalanCeD proof-of-concept study is specifically testing asedebart in Cushing’s disease. That difference reflects the broader biological role of ACTH across several forms of endogenous hypercortisolism.
Cushing’s disease arises from a pituitary source, but ACTH-dependent Cushing’s syndrome can also result from tumors elsewhere in the body that produce ACTH ectopically. In principle, an antibody targeting circulating ACTH could be relevant irrespective of whether the excessive hormone originates in the pituitary or another tumor, although each population may have different disease dynamics and evidence requirements.
Asedebart would be less logically suited to ACTH-independent disease in which cortisol production is driven directly by the adrenal gland rather than excessive ACTH stimulation. Final clinical development and any eventual regulatory indication will therefore need to align closely with the biological populations in which the drug has actually been studied.
Lundbeck is also evaluating the same antibody in classic congenital adrenal hyperplasia, another condition characterized by chronically elevated ACTH. The company has already secured orphan designations for asedebart in congenital adrenal hyperplasia in several jurisdictions, suggesting that management sees ACTH neutralization as a broader rare-endocrine platform rather than a single-indication program.
That strategy could improve the commercial value of the molecule if proof of mechanism translates across ACTH-driven disorders. It also increases the need to understand long-term suppression of the hypothalamic-pituitary-adrenal axis in different disease contexts.
What must Lundbeck establish before asedebart can become a credible registrational program?
The next step is a more complete understanding of dose response. An antibody used in a hormone disorder needs enough pharmacological precision to prevent patients cycling between uncontrolled hypercortisolism and excessive cortisol suppression. The ideal regimen would maintain biochemical control over an extended dosing interval with relatively predictable adjustment requirements.
Lundbeck will also need to show that urinary free cortisol normalization aligns with improvement in other biochemical and clinical measures. Blood pressure, glucose metabolism, body composition, muscle function, neuropsychiatric symptoms and quality of life could all become important when judging whether biochemical control is translating into meaningful benefit.
Durability is another unresolved issue. Cushing’s disease is chronic, and patients who cannot achieve sustained surgical remission may require prolonged medical therapy. Antibody treatment would therefore need to maintain effect without problematic immunogenicity, loss of response or cumulative adverse events.
The eventual delivery method could materially influence adoption. Intravenous titration may be useful during early development because it allows controlled exposure, but a practical long-term therapy would generally benefit from a convenient subcutaneous regimen that can be integrated into chronic disease management.
Regulatory discussions will determine what size and type of confirmatory program Lundbeck needs after proof of concept. Orphan status can support development efficiency, but it does not remove the obligation to demonstrate a favorable benefit-risk profile.
The September designation is therefore a useful milestone rather than the central value inflection point for asedebart. Lundbeck has regulatory recognition that endogenous Cushing’s syndrome qualifies as a rare disease area suitable for orphan incentives and early human evidence that direct ACTH neutralization can lower cortisol. The more consequential question is whether that mechanism can provide stable, clinically meaningful control over a disease in which small changes in endocrine balance can have significant consequences.