Raidium has appointed Stanford University radiologist and artificial intelligence researcher Curtis Langlotz to its strategic advisory board, strengthening the company’s clinical expertise as it develops AI-assisted radiology reporting technology. Announced on 6 November 2026, the appointment will focus on clinical validation, responsible system development and maintaining radiologist oversight as increasingly capable imaging models enter healthcare workflows.
The appointment comes at a critical point for medical imaging artificial intelligence, where technical performance is advancing faster than the evidence needed to establish routine clinical utility. While imaging foundation models can support detection, segmentation, measurement and report generation, their usefulness in everyday clinical practice depends on whether they can deliver consistent, clinically accurate outputs across different patient populations and hospital environments.
For Raidium, which is building a unified imaging platform around foundation models and radiologist-controlled workflows, Langlotz brings expertise directly relevant to the transition from research demonstrations towards dependable clinical applications. The company’s challenge is no longer limited to developing algorithms that recognise imaging features. It must demonstrate that multiple AI functions can work together without introducing errors, increasing reporting uncertainty or undermining clinical accountability.
Why has Raidium appointed Curtis Langlotz as clinical scrutiny of AI radiology reporting increases?
Curtis Langlotz is Professor of Radiology, Medicine and Biomedical Data Science at Stanford University and director of its Center for Artificial Intelligence in Medicine and Imaging. His research encompasses machine learning for medical image interpretation, diagnostic accuracy, healthcare information systems and AI-supported clinical communication. His appointment gives Raidium access to expertise spanning algorithm development, radiology workflow design and the evaluation of AI in clinical settings.
According to the company, Langlotz will advise on the clinical validation and responsible development of AI-assisted radiology reporting. He has emphasised that the reliability of imaging AI should be assessed at the level of the complete clinical system rather than through isolated measures of model accuracy. That approach considers how software processes images, how information is presented to radiologists and how clinicians review and correct generated outputs.
The distinction is particularly relevant to generative AI systems that produce draft imaging reports. An algorithm may successfully identify abnormalities while still generating incomplete descriptions, inconsistent measurements or misleading conclusions when converting visual findings into clinical language. Even technically accurate outputs can become problematic if relevant clinical context is missing or radiologists cannot easily establish which observations support the suggested interpretation.
Langlotz has worked on related challenges through research involving automated report drafting and tools intended to improve understanding of radiology findings. His involvement could help Raidium develop validation frameworks that account for both algorithm performance and the human decisions surrounding AI-generated reports. However, the appointment itself does not constitute clinical validation, regulatory authorisation or proof that the company’s reporting software improves patient outcomes.
How does Raidium’s Curia foundation model support its wider medical imaging AI strategy?
Raidium is developing an integrated radiology technology platform built around foundation models trained on large collections of medical imaging data. Its Curia research programme focuses on extracting broadly applicable imaging representations rather than developing an entirely separate algorithm for every anatomical structure or diagnostic task. The company has reported training its original Curia model on more than 200 million computed tomography and magnetic resonance imaging slices.
The underlying commercial proposition is that a sufficiently capable foundation model could support multiple imaging functions within a unified workflow. These include identifying anatomical structures, segmenting lesions, measuring abnormalities, comparing current and previous examinations and helping prepare structured findings. By bringing these tasks together, Raidium is seeking to reduce the fragmentation that arises when radiologists must navigate separate software applications for different aspects of image interpretation.
The company has also advanced its research through Curia-2 and its Jolia family of vision-language models. The latter work is particularly relevant to reporting because it aims to connect features visible on medical scans with the clinical terminology used to describe them. This moves beyond image recognition towards systems that associate anatomical observations with meaningful radiological language.
However, the clinical implications of these capabilities depend on their evaluation. Performance across selected image classification, segmentation or reporting benchmarks cannot automatically establish reliability in hospitals where image quality, equipment, acquisition protocols and disease presentations vary considerably. Raidium has indicated that peer-reviewed publication of its Curia research is forthcoming, while its existing research portfolio includes published and preliminary work across imaging applications.
What does Raidium Read’s deployment in oncology imaging reveal about the commercial opportunity?
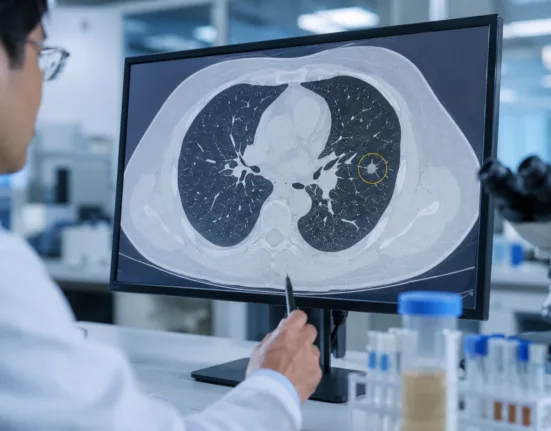
Raidium has already taken an initial step beyond laboratory research through its Raidium Read oncology imaging platform. In July 2026, the company announced the platform’s US launch targeting oncology research centres and disclosed deployment at Moffitt Cancer Center, where it was selected to replace an existing radiomics tool. The platform supports imaging review activities such as lesion detection, segmentation and comparison of abnormalities across successive examinations.
Cancer imaging represents a potentially valuable initial application because treatment assessment often requires detailed examination of multiple lesions across several anatomical locations and imaging time points. Radiologists and research teams must establish whether individual lesions have changed, whether new abnormalities have appeared and whether measurements satisfy defined response criteria. These tasks can require considerable manual effort, particularly in longitudinal oncology studies.
Raidium Read is designed to support these activities, including workflows associated with Response Evaluation Criteria in Solid Tumours, commonly known as RECIST. Automated identification and longitudinal tracking of lesions could improve workflow consistency if the software maintains measurement accuracy and enables users to inspect its outputs. Such capabilities may be useful to cancer research organisations, pharmaceutical developers and imaging teams responsible for treatment-response assessments.
Nevertheless, deployment within a cancer research environment is different from establishing broad clinical utility in routine diagnostic practice. The company has not demonstrated through the appointment announcement that its technology reduces diagnostic errors, improves clinical outcomes or produces verified efficiency gains across multiple hospitals. The evidence required for these claims would need to assess measurable clinical and operational endpoints under representative conditions.
The research setting also has distinct purchasing and implementation requirements. Oncology trials may place substantial value on reproducible lesion measurements and auditability, while diagnostic radiology departments must additionally consider reporting turnaround, patient safety, integration with clinical records and compatibility with established image-management systems. Success in one setting can inform broader development, but does not eliminate the need for separate evaluation.
Why is clinical validation more demanding for generative AI reporting than conventional imaging algorithms?
Traditional medical imaging algorithms are frequently designed around a relatively narrow question, such as detecting a specific abnormality or identifying an anatomical structure. Their performance can often be characterised through established measures including sensitivity, specificity and agreement with expert reference standards. Generative reporting systems face a more complex problem because they combine image interpretation with language production and clinical communication.
A report may contain several clinically important observations that must be represented accurately and in the correct context. Errors can arise through omitted findings, incorrect anatomical descriptions, unsupported diagnostic statements or inconsistencies between the findings section and the final impression. An apparently fluent report is therefore not necessarily an accurate or clinically useful one.
Independent research has illustrated both the potential and limitations of AI-assisted reporting. A study published in the Journal of the American College of Radiology in 2026 examined 756 chest radiographs interpreted by five radiologists using AI-generated preliminary reports. Reading times declined across successive study batches, although report agreement and quality varied, particularly for abnormal examinations.
Those findings support further investigation of clinician-supervised draft reporting, but they cannot be transferred directly to Raidium’s products. The study involved a different AI system and a defined image interpretation task. Establishing comparable performance for Raidium would require validation of its own software, including the reporting functions and clinical workflows for which it seeks deployment.
For comprehensive assessment, studies would need to capture not only whether AI-generated reports resemble expert-written reports but also whether radiologists identify and correct consequential errors. Error severity, correction time, reporting consistency, clinically relevant omissions and the possibility of automation bias are important considerations. Prospective studies could then determine whether any efficiency gains persist without compromising diagnostic quality.
How could radiologist oversight and explainable AI influence hospital adoption?
Raidium has emphasised that its technology is intended to keep radiologists in control of clinical reporting. Langlotz has similarly identified the importance of allowing clinicians to understand how a proposed report was produced and retain responsibility for the conclusions they approve. This places explainability and human oversight at the centre of the company’s development strategy.
In practical terms, radiologists need mechanisms to check the relationship between an AI-generated statement and the underlying images. A system that highlights the relevant lesion, measurement or image region may be easier to review than one that provides a polished narrative without accessible supporting evidence. Such design choices could also influence how quickly clinicians can detect errors and resolve disagreements.
Hospital adoption will depend on the platform’s ability to work within existing picture archiving and communication systems, radiology information systems and electronic health records. Software that requires extensive switching between applications could undermine productivity gains, even when its individual algorithms perform well. Cybersecurity, patient-data governance, model-update controls and the availability of technical support will also influence procurement decisions.
The regulatory pathway represents another consideration. In the United States, whether a software function requires Food and Drug Administration oversight depends on its intended use, functionality and applicable regulatory classification. Raidium’s November announcement does not establish a new FDA clearance for its reporting technology, and its research deployment should not be interpreted as authorisation for unrestricted clinical diagnosis.
Professional expectations are also developing. In May 2026, the American College of Radiology approved a practice parameter addressing the selection, implementation, monitoring and continuous improvement of imaging AI. This reinforces the importance of evaluating software after deployment rather than relying exclusively on performance reported before installation.
Can Raidium convert its clinical advisory expertise into a stronger position in radiology AI?
The commercial opportunity for integrated radiology AI platforms extends beyond automating individual image-analysis tasks. Hospitals and imaging providers increasingly need systems capable of coordinating detection, measurement, reporting and quality assurance while operating within existing clinical infrastructure. A unified platform could become attractive if it reduces technology fragmentation and delivers independently demonstrated workflow benefits.
Raidium’s strategy places its foundation-model research alongside a clinical interface designed around radiologist interaction. Its oncology research deployment provides an initial setting in which the company can gather implementation experience, while the addition of Langlotz strengthens the expertise available to guide future validation. Neither development establishes how widely the platform will be purchased or whether its performance will translate across different clinical environments.
The company must also navigate a competitive market containing established imaging software suppliers, specialised AI developers and healthcare technology companies expanding their own algorithm capabilities. Hospitals are unlikely to evaluate a new system solely on the sophistication of its underlying model. They will examine clinical evidence, integration costs, service reliability, vendor sustainability and the extent to which the technology improves existing workflows.
One particularly important question is whether generative reporting should be treated as a standalone product or as an extension of verified image-analysis functions. The latter approach could allow Raidium to connect generated text directly with identifiable measurements and anatomical findings. However, the company would still need to demonstrate that combining these functions does not introduce additional clinical errors.
Raidium has scheduled a webinar on 10 November 2026 involving Langlotz to discuss the use and future of AI in radiology. The event may provide further insight into the company’s approach to clinician oversight and validation, although a scientific presentation or discussion does not replace formal clinical evidence.
For Raidium, the appointment strengthens an important aspect of its development strategy at a time when clinical validation standards are becoming more demanding. Its next meaningful achievements will be independently assessed performance, transparent reporting of errors and prospective evidence demonstrating that radiologists can use its systems effectively. Those outcomes, rather than the advisory appointment alone, will determine whether Raidium can progress from promising imaging AI research towards sustained clinical adoption.