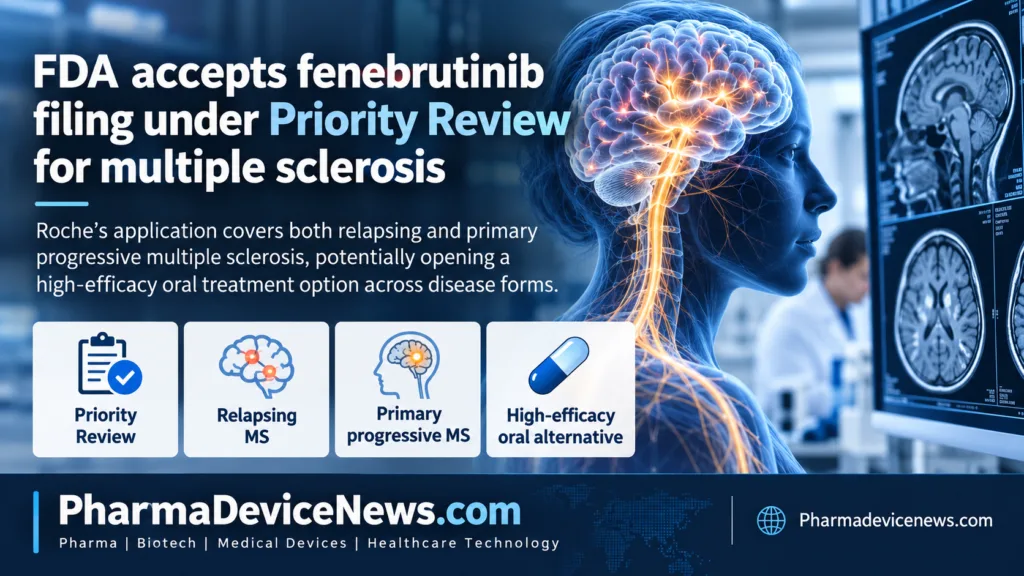
Roche Holding AG has moved one of its most important neuroscience pipeline assets into United States regulatory review after the Food and Drug Administration accepted fenebrutinib for both relapsing multiple sclerosis and primary progressive multiple sclerosis, with the filing receiving Priority Review. The September 30 milestone puts the experimental oral Bruton’s tyrosine kinase inhibitor on a potential path toward becoming the first BTK inhibitor approved across both major forms of multiple sclerosis, following three positive Phase 3 studies covering more than 2,000 patients.
The filing is supported by FENhance 1 and FENhance 2, where fenebrutinib reduced annualized relapse rates by 51.1% and 58.5%, respectively, compared with teriflunomide in patients with relapsing multiple sclerosis. Roche said those rates equated to approximately one relapse every 17 years among fenebrutinib-treated patients during the study period. The regulatory package also includes FENtrepid, where the oral drug demonstrated non-inferiority to Roche’s own Ocrevus in slowing disability progression among patients with primary progressive multiple sclerosis.
That makes fenebrutinib strategically unusual. Roche is not developing the medicine simply to attack a rival franchise. If approved, it could compete partly against Ocrevus, one of Roche’s largest existing products, which generated CHF3.47 billion in first-half 2026 sales and grew 7% at constant exchange rates. The company is effectively betting that a high-efficacy oral medicine capable of targeting both acute inflammatory disease and chronic neurological progression can expand its overall multiple sclerosis franchise even if some patients eventually switch from another Roche therapy.
Why could fenebrutinib become a different kind of multiple sclerosis medicine?
Multiple sclerosis treatment has traditionally required physicians to balance efficacy, safety and convenience. Some highly effective therapies involve infusions or injections, while several oral medicines are easier to administer but may be positioned differently because of efficacy, safety or monitoring considerations.
Fenebrutinib is designed to challenge that trade-off. The small molecule crosses the blood-brain barrier and inhibits Bruton’s tyrosine kinase, an enzyme involved in both B-cell activity in the peripheral immune system and microglial activity inside the central nervous system. Roche believes that dual action could allow the drug to address inflammatory relapses while also influencing chronic processes associated with disability progression.
The distinction matters because multiple sclerosis does not consist only of visible relapses. Patients can accumulate neurological disability even when overt attacks become less frequent. A medicine capable of suppressing inflammatory activity while simultaneously affecting disease mechanisms within the brain could therefore address a larger portion of the disease than treatments focused predominantly on peripheral immune activity.
Fenebrutinib is also reversible and non-covalent, unlike several other BTK inhibitors that form permanent chemical bonds with their target. Roche has reported that the molecule is approximately 130 times more selective for BTK than other kinases, a pharmacological characteristic the company believes could help limit unwanted off-target activity. Whether that biochemical differentiation translates into a clinically superior long-term safety profile will ultimately depend on regulatory review and post-approval experience rather than mechanism alone.
How convincing are the 51% and 58.5% relapse reductions in relapsing MS?
FENhance 1 and FENhance 2 collectively enrolled approximately 1,500 adults with relapsing multiple sclerosis and compared twice-daily oral fenebrutinib with once-daily teriflunomide for at least 96 weeks. Both studies met their primary endpoints, with fenebrutinib reducing annualized relapse rates by 51.1% in FENhance 1 and 58.5% in FENhance 2.
Roche also reported significant reductions in active brain lesions on magnetic resonance imaging and favorable trends across disability-progression measures. The consistency between two separately conducted pivotal trials strengthens the efficacy case because the result does not depend on a single unusually favorable study population.
The comparator requires context, however. Teriflunomide is an established oral multiple sclerosis therapy, but modern relapsing MS treatment also includes highly effective anti-CD20 therapies such as Ocrevus, Novartis’ Kesimpta and TG Therapeutics’ Briumvi. Fenebrutinib did not directly demonstrate superiority to those high-efficacy medicines in FENhance 1 or FENhance 2.
That means the 51% to 58.5% relapse reductions are clinically meaningful but do not establish that fenebrutinib is the most effective therapy available for relapsing disease. The commercial opportunity will depend partly on whether physicians view its combination of efficacy, oral administration and central nervous system penetration as sufficiently compelling relative to established injectable and infused treatments.
Why may primary progressive multiple sclerosis be the bigger strategic opportunity?
Primary progressive multiple sclerosis represents roughly 15% of the multiple sclerosis population and differs from relapsing disease because neurological disability typically worsens steadily without clearly separated attacks and remissions. Treatment options are particularly limited, with Ocrevus remaining the only approved disease-modifying therapy for primary progressive MS.
FENtrepid therefore used an unusually demanding comparator. Instead of testing fenebrutinib against placebo, Roche compared the oral drug directly with Ocrevus in 985 adults with primary progressive disease.
Fenebrutinib met the study’s primary non-inferiority endpoint on 12-week composite confirmed disability progression. The numerical result favored fenebrutinib, with a 12% lower risk of disability progression than Ocrevus, but the confidence interval crossed one, meaning the trial did not establish statistical superiority on that endpoint. Roche also reported a 26% reduction in the risk of worsening upper-limb function measured through the nine-hole peg test.
That distinction is essential. Fenebrutinib showed that an oral BTK inhibitor could perform at least comparably with the only approved PPMS disease-modifying medicine in a pivotal trial, but the reported 12% numerical advantage should not be described as proven superiority over Ocrevus.
Even non-inferiority could nevertheless have substantial commercial consequences. Ocrevus requires healthcare-professional administration, while fenebrutinib is an oral treatment. If regulators determine the benefit-risk profile is favorable, some patients and physicians could prefer a high-efficacy oral alternative to recurring infusion or injection procedures.
Could Roche end up cannibalizing its own Ocrevus franchise?
Yes, but that may be preferable to allowing another company to do it.
Ocrevus remains a major growth product for Roche. First-half 2026 sales reached CHF3.47 billion, including CHF2.30 billion in the United States and CHF758 million in Europe. Revenue increased 7% at constant exchange rates overall, while international sales climbed 30%.
The franchise has also evolved beyond traditional intravenous infusion through Ocrevus Zunovo, a subcutaneous formulation designed to make administration faster and more convenient. Roche is therefore improving Ocrevus at the same time that it develops fenebrutinib.
This creates a portfolio strategy rather than a simple replacement strategy. Some patients may prefer infrequent healthcare-professional-administered anti-CD20 treatment, while others may value oral therapy. Patients with primary progressive disease could gain a second mechanism, and physicians may eventually sequence or select treatment according to disease activity, age, infection risk, convenience and individual preferences.
Large pharmaceutical companies often benefit from disrupting themselves. If oral BTK inhibition eventually takes share from anti-CD20 therapy, Roche would rather retain part of that economic value through fenebrutinib than watch a rival company capture it.
What safety questions will the FDA examine most closely?
Safety is the most important unresolved part of the fenebrutinib story.
In FENtrepid, liver enzyme elevations occurred more frequently with fenebrutinib than Ocrevus, at 13.3% versus 2.9%. Roche described the elevations as transient and reversible after treatment discontinuation, with no Hy’s Law cases indicating severe drug-induced liver injury. Serious adverse events occurred in 19.1% of fenebrutinib recipients compared with 18.9% receiving Ocrevus.
Fatal events also deserve attention. FENtrepid reported deaths in 1.4% of patients receiving fenebrutinib compared with 0.2% in the Ocrevus arm. Investigators assessed the deaths as unrelated to study treatment and Roche said no pattern was observed in timing or cause, but the imbalance remains part of the evidence regulators must consider.
Reuters previously reported that across Roche’s relapsing-MS studies, deaths were also numerically higher among fenebrutinib-treated patients than those receiving teriflunomide, with infections among the events investigators considered potentially treatment related. Roche maintained that the overall benefit-risk profile remained supportive of regulatory submission.
BTK inhibitors as a class have also faced scrutiny around liver toxicity. Several clinical programs have encountered regulatory holds or enhanced monitoring because of elevated liver enzymes, meaning fenebrutinib’s hepatic profile will receive careful examination even though Roche has not reported Hy’s Law cases in the pivotal MS studies.
The FDA’s acceptance of the application under Priority Review indicates that the agency considers the filing sufficiently complete for review and potentially significant to patient care. It does not mean the agency has concluded that safety concerns are resolved or that approval is assured.
How does fenebrutinib compare with Novartis’ remibrutinib race?
Roche is not alone in pursuing BTK inhibition for multiple sclerosis. Novartis recently reported positive Phase 3 REMODEL-1 and REMODEL-2 trials for remibrutinib in relapsing MS, creating the prospect that two major pharmaceutical companies could compete to establish BTK inhibition as a new oral treatment class.
The development strategies are not identical. Novartis’ pivotal evidence currently centers on relapsing multiple sclerosis, while Roche has generated positive Phase 3 evidence across both relapsing and primary progressive disease.
That PPMS dataset could become Roche’s strongest differentiation because progressive MS remains one of the most difficult areas in neurology. Fenebrutinib’s direct comparison with Ocrevus also provides evidence against a high-efficacy benchmark that is absent from many oral multiple sclerosis development programs.
Safety could ultimately determine competitive positioning as much as efficacy. An oral therapy offering strong relapse control is attractive, but neurologists treating a chronic disease may be reluctant to trade administration convenience for significant liver monitoring or other serious adverse events.
The first BTK inhibitor to achieve approval may gain visibility, but the larger commercial winner will likely be determined by long-term efficacy, disability data, safety, monitoring burden and physician confidence rather than launch timing alone.
What could FDA approval mean for Roche’s neuroscience business?
Roche’s first-half 2026 sales reached CHF30.36 billion, up 6% at constant exchange rates, while Pharmaceuticals sales increased 6% to CHF23.63 billion. Ocrevus was one of the company’s five largest growth drivers, reinforcing the financial importance of maintaining leadership in multiple sclerosis as competing anti-CD20 medicines and new oral mechanisms advance.
Fenebrutinib gives Roche a potential growth bridge within a therapeutic area where it already has strong commercial infrastructure. The company does not need to build new relationships with neurologists, multiple sclerosis centers or payers from scratch. Instead, it can add another mechanism to a franchise already supported by years of Ocrevus prescribing experience.
Management has recently indicated that a fenebrutinib launch could come in early 2027 if regulatory review proceeds successfully. That timeline would put the medicine among Roche’s most important near-term pipeline launches alongside oncology, immunology and other neuroscience assets.
The opportunity is also strategically defensive. Ocrevus will remain important, but pharmaceutical markets increasingly reward companies capable of offering several treatment modalities rather than defending one blockbuster indefinitely.
What is the latest sentiment around Roche shares?
Roche participation certificates closed at CHF353.70 in Zurich on September 29, down 0.48% for the session after falling 1.36% a day earlier. The shares had traded at CHF364.80 on September 21, meaning some of the gains seen earlier in the month had been surrendered before the latest fenebrutinib regulatory milestone.
The movement cannot be attributed specifically to fenebrutinib. Roche investors are simultaneously assessing multiple major pipeline programs, oncology launches, the obesity portfolio, diagnostics growth, currency effects and management’s longer-term guidance.
The regulatory acceptance nevertheless removes one development uncertainty. Fenebrutinib is no longer merely a positive Phase 3 program waiting to enter the FDA process. It is now a formally reviewed asset with the potential to add another commercially significant franchise to Roche’s neurological portfolio.
What should physicians and investors watch next for fenebrutinib?
The FDA’s final assessment of safety will be the decisive issue. The efficacy package is substantial: two relapsing-MS trials independently showed roughly 51% to 59% reductions in relapse rates versus teriflunomide, while the PPMS program demonstrated non-inferiority against Ocrevus on disability progression. The question is whether those benefits outweigh liver abnormalities, infection concerns and the numerical imbalances in deaths observed across parts of the program.
Label breadth will matter almost as much as approval itself. Authorization across both relapsing and primary progressive disease would give Roche something unusual: an oral therapy capable of operating across a much wider spectrum of multiple sclerosis than most existing medicines.
Commercial adoption would then become the next test. Neurologists will have to decide whether fenebrutinib should compete primarily with existing oral treatments or whether its efficacy is strong enough to challenge infused and injected high-efficacy therapies.
That is what makes the September 30 filing acceptance commercially important. Roche is not simply attempting to launch another multiple sclerosis pill. It is asking regulators to approve an oral medicine that could sit beside, and potentially compete against, one of Roche’s own most successful franchises while opening the first serious oral treatment option for primary progressive multiple sclerosis.