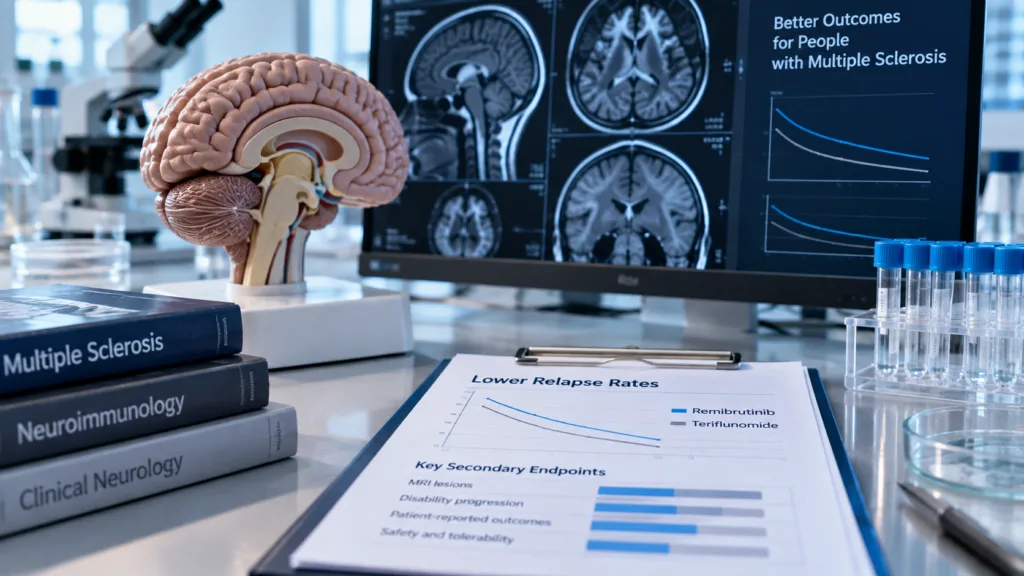
Novartis has delivered an important late-stage win in multiple sclerosis after remibrutinib met the primary endpoint in both Phase 3 REMODEL trials, significantly reducing annualized relapse rates compared with teriflunomide while also outperforming the established oral therapy across all key secondary endpoints within each study. The Swiss pharmaceutical group has not yet released the exact relapse-rate reductions, but it plans a late-breaking presentation at MSToronto2026 and intends to submit remibrutinib to regulators globally.
The result is notable because remibrutinib belongs to the Bruton’s tyrosine kinase inhibitor class, one of the most closely watched but technically difficult areas of multiple sclerosis drug development. Several developers have pursued BTK inhibition in hopes of affecting immune activity both outside and potentially within the central nervous system, but clinical setbacks and safety concerns have prevented the mechanism from producing the simple breakthrough once anticipated.
Novartis now has two successful pivotal relapsing multiple sclerosis studies. REMODEL-1 and REMODEL-2 both showed significant reductions in annualized relapse rate and inflammatory brain lesions, while a prespecified combined analysis produced a positive trend in three-month confirmed disability progression and nominally significant improvement in six-month confirmed disability progression. Crucially, Novartis reported no liver-safety signal and no cases meeting Hy’s Law criteria across a broader remibrutinib development program involving more than 4,500 participants.
Why is the disability signal more important than simply reducing multiple sclerosis relapses?
Modern multiple sclerosis treatment has become highly effective at suppressing relapses and magnetic-resonance-imaging activity. The harder therapeutic objective is preventing the gradual accumulation of disability that can continue even when obvious inflammatory attacks become less frequent.
That distinction helps explain industry interest in BTK inhibitors. Bruton’s tyrosine kinase is involved in B-cell signaling and myeloid-cell activity, creating a theoretical opportunity to influence aspects of disease biology that differ from conventional therapies focused primarily on peripheral lymphocytes.
Remibrutinib has not yet established that it fundamentally changes progressive multiple sclerosis biology. Novartis reported a favorable disability signal in the pooled REMODEL analysis, but the exact magnitude and statistical hierarchy will need to be evaluated when full results are presented. A positive trend in three-month confirmed disability progression is not equivalent to a formally significant result, while nominal significance at six months needs to be interpreted within the trial’s multiplicity-testing structure.
Still, evidence of sustained disability benefit would substantially strengthen the commercial proposition because physicians already have many options capable of reducing relapses. The more remibrutinib can differentiate on disability, safety and convenience, the easier it becomes to justify switching patients from established drugs.
Why does the absence of a liver-safety signal matter for Novartis?
BTK drug development has faced intense scrutiny around hepatic safety. That creates a class-level perception problem even when compounds differ in selectivity, pharmacology and dosing.
Novartis therefore highlighted that remibrutinib showed no liver-safety signal in REMODEL-1 and REMODEL-2 and no Hy’s Law cases across its broader clinical development program. The finding is especially relevant because chronic multiple sclerosis therapies may be taken for many years, meaning regulators and physicians have a low tolerance for serious organ toxicity when alternative treatments are available.
Safety differentiation can become commercially powerful in chronic disease. A drug does not necessarily need to produce dramatically greater efficacy if it combines strong disease control with convenient oral administration and a monitoring burden that is easier for physicians and patients to manage.
Remibrutinib is already familiar to Novartis through its development in chronic spontaneous urticaria, giving the company a larger safety database than would exist for a molecule being tested exclusively in neurological disease. That cross-indication exposure does not eliminate multiple sclerosis-specific risks but gives regulators additional experience with the molecule.
How would remibrutinib fit alongside Novartis’ existing multiple sclerosis franchise?
Novartis is not entering multiple sclerosis as an outsider. Its Kesimpta franchise already provides a high-efficacy B-cell-directed treatment, and second-quarter 2026 Kesimpta sales increased 32% at constant currencies. That means remibrutinib could broaden the company’s neurological portfolio while simultaneously creating an internal positioning challenge.
Kesimpta is administered by subcutaneous injection, while remibrutinib is oral. Those routes naturally appeal to different patients, but treatment decisions also depend on disease activity, safety, pregnancy considerations, immune suppression, laboratory monitoring and physician preference.
If remibrutinib ultimately provides strong relapse control with meaningful disability benefit and favorable safety, Novartis could potentially span several treatment intensities rather than relying on a single approach. That may prove more valuable than simply replacing Kesimpta prescriptions because the multiple sclerosis market is large enough to support segmentation.
The company will need to demonstrate where remibrutinib sits relative to other high-efficacy treatments rather than only teriflunomide, an established oral comparator. Beating an older therapy is sufficient for pivotal evidence but does not automatically establish superiority over the most effective modern options.
Why is this pipeline success particularly important for Novartis now?
Novartis’ investor narrative has recently been complicated by the failure of the Phase 3 Lp(a)HORIZON cardiovascular study of pelacarsen. The setback triggered a sharp share-price decline in early September and raised questions about the value of one of the company’s prominent cardiovascular pipeline programs.
That makes successful late-stage programs elsewhere more valuable. Novartis reported only 1% constant-currency sales growth in the second quarter, although several priority products were growing rapidly, including Kisqali, Kesimpta, Scemblix, Pluvicto and Leqvio. The company maintained its 2026 guidance for low-single-digit sales growth despite a more difficult first half.
Remibrutinib therefore arrives as evidence that the pipeline is not defined by one cardiovascular failure. Investors have subsequently shown some willingness to look through the pelacarsen setback, with Novartis shares trading higher again by September 16 as analysts assessed the remaining growth portfolio.
The commercial value cannot yet be modeled precisely because Novartis has not disclosed the complete REMODEL dataset, regulators have not reviewed it, and pricing or launch timing remains unknown. But two successful Phase 3 trials substantially reduce development risk.
What should physicians watch in the full REMODEL presentation?
The exact annualized relapse rates are the most obvious missing numbers. Relative reductions are useful, but absolute relapse rates will show how much disease activity remained in both groups.
MRI lesion data will provide another measure of inflammatory control, while disability curves will deserve particularly close examination. A convincing six-month confirmed disability result would be more clinically meaningful than short-lived differences that disappear as follow-up continues.
Safety details should include liver enzymes, infections, cardiovascular events and treatment discontinuations. With chronic immunomodulatory therapies, a favorable top-line safety statement becomes far more persuasive once event frequencies and exposure-adjusted rates are visible.
Novartis also needs to explain how remibrutinib will be positioned against Kesimpta and other highly effective multiple sclerosis therapies. Oral administration is an advantage, but efficacy expectations in relapsing disease are now high.
The two REMODEL wins nevertheless give Novartis something the BTK class has often lacked: replicated Phase 3 efficacy with an apparently favorable hepatic-safety profile. Full data will determine whether that is sufficient to turn remibrutinib from an interesting mechanism into a commercially important multiple sclerosis medicine.