CSL Seqirus has published Phase 3 results from a 7,699-person randomized study evaluating an MF59-adjuvanted, cell-derived, higher-dose quadrivalent influenza vaccine in adults aged 50 years and older, providing the most detailed late-stage evidence yet for a strategy that combines three established methods of strengthening seasonal flu vaccination within one product. The vaccine produced stronger immune responses than an adjuvanted egg-based comparator across all four tested influenza strains, while meeting non-inferiority criteria against a recombinant vaccine for three of four strains overall.
The exception is important. Against the recombinant comparator, the investigational vaccine failed the prespecified non-inferiority threshold for A/H3N2 in the overall population aged 50 and older, despite meeting it for A/H1N1 and both B strains. That prevents the Phase 3 program from being reduced to a simple claim that combining a higher antigen dose, cell-based manufacturing and MF59 adjuvant universally outperforms other enhanced influenza vaccines.
The peer-reviewed study, published in The Lancet Infectious Diseases, primarily evaluates immune responses and safety rather than laboratory-confirmed influenza illness, hospitalization or mortality. It therefore provides strong comparative immunogenicity evidence but does not independently prove that the new formulation prevents more influenza cases than its active comparators.
A related trivalent formulation is already marketed as AUJEMFLU and has received authorization in the European Union and United Kingdom for prevention of influenza in adults aged 50 and older. The distinction between that licensed trivalent product and the quadrivalent vaccine used in the published trial is important when interpreting what exactly regulators have authorized.
Why combine higher antigen dose, MF59 adjuvant and cell-based manufacturing in one influenza vaccine?
Older adults are disproportionately affected by severe influenza but also tend to generate weaker immune responses to vaccination because immune function changes with age. Vaccine developers have consequently pursued several strategies intended to compensate for immunosenescence.
One approach increases the amount of influenza antigen presented to the immune system. Higher-dose vaccines provide more haemagglutinin antigen per strain than standard formulations, creating a stronger stimulus for antibody production.
A second approach uses an adjuvant. CSL Seqirus has decades of experience with MF59, an oil-in-water adjuvant containing squalene that is intended to enhance and broaden the immune response to influenza antigens.
The third approach changes how the vaccine virus antigens are produced. Traditional influenza vaccines frequently rely on eggs, but growth in eggs can introduce adaptive changes in the viral proteins that may make the vaccine antigen less closely matched to circulating viruses. Cell-based manufacturing reduces that particular source of adaptation.
Each strategy already has an independent clinical history. CSL Seqirus’ development thesis is that combining all three in one vaccine may produce broader or stronger immunity than relying on only one enhancement method.
The Phase 3 study was designed to test whether those theoretical advantages remain measurable when the combined product is compared directly with other enhanced vaccines rather than with a basic standard-dose shot.
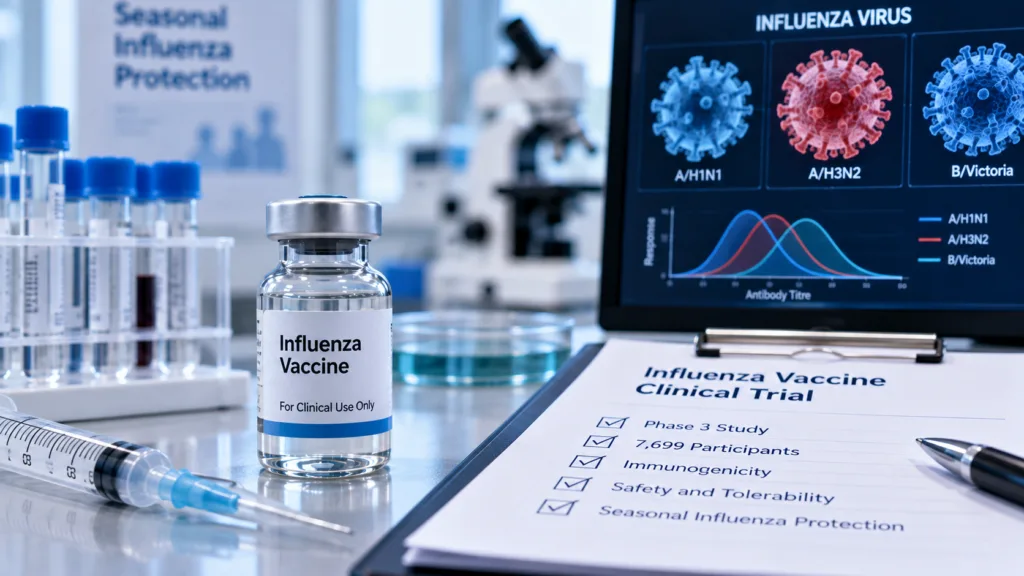
What did the 7,699-person Phase 3 trial actually show?
The randomized, observer-blind study enrolled adults aged 50 and older across eight countries. Participants were assigned to receive the investigational adjuvanted cell-derived higher-dose quadrivalent vaccine, an MF59-adjuvanted egg-derived quadrivalent vaccine or a higher-dose recombinant quadrivalent vaccine.
The investigational vaccine contained 45 micrograms of haemagglutinin antigen per influenza strain and 19.5 milligrams of squalene in the MF59 adjuvant. The egg-derived adjuvanted comparator contained 15 micrograms of antigen per strain and half that amount of MF59, while the recombinant comparator also provided 45 micrograms of antigen per strain without MF59.
The trial first examined manufacturing consistency across three lots of the investigational vaccine, an important regulatory requirement because large-scale vaccine production must generate reproducible immune responses across batches. The predefined lot-to-lot consistency criteria were met.
Against the adjuvanted egg-based vaccine, the combined cell-based higher-dose formulation met non-inferiority and demonstrated statistically higher geometric mean antibody titers against all four strains assessed. The geometric mean titer ratios were approximately 1.53 for A/H1N1, 1.22 for A/H3N2, 1.73 for B/Victoria and 1.71 for B/Yamagata.
Seroconversion differences also favored the investigational vaccine across the four strains, supporting the interpretation that its enhanced formulation produced stronger measured antibody responses than the lower-dose adjuvanted egg-based comparator.
Why does the A/H3N2 miss against the recombinant vaccine deserve attention?
The recombinant comparator sets a tougher benchmark because it already contains a higher antigen dose and avoids egg-based production. In that comparison, CSL Seqirus’ formulation met non-inferiority requirements for A/H1N1, B/Victoria and B/Yamagata but narrowly failed the prespecified geometric mean titer criterion for A/H3N2.
The A/H3N2 geometric mean titer ratio was approximately 0.69, with the lower bound of the 97.5% confidence interval at about 0.65. The trial required the lower confidence bound to remain at or above 0.67 to establish non-inferiority, leaving the result just outside the specified statistical threshold.
This should not be interpreted as evidence that the vaccine provides no protection against H3N2. It means that one predefined comparative immunogenicity objective against the recombinant vaccine was not satisfied in the overall 50-and-older population.
H3N2 has historically been a particularly difficult influenza subtype for vaccination because it evolves rapidly and has presented challenges around antigenic match. The finding reinforces why vaccine performance needs to be considered strain by strain rather than summarized through one average immune-response number.
CSL Seqirus also reported that the non-inferiority picture differed in older subgroups, with comparisons appearing stronger among adults aged 65 and above. Those analyses can be informative, but prespecified primary endpoints in the full analysis population remain the most appropriate foundation for interpreting the trial.
Does stronger immunogenicity prove that the vaccine prevents more influenza cases?
No. Antibody titers provide an accepted and useful measure of vaccine immunogenicity, particularly for regulatory comparison and manufacturing consistency, but they are not identical to clinical vaccine effectiveness.
The Phase 3 study was not primarily designed to show fewer laboratory-confirmed influenza cases, hospitalizations or deaths between vaccine groups. A product can produce higher antibody titers without the trial directly establishing a corresponding percentage reduction in clinical illness.
This distinction matters when describing comparative performance. The published data support a conclusion that the investigational vaccine generated stronger measured immune responses than the adjuvanted egg-based comparator and met most of the non-inferiority comparisons against the recombinant vaccine.
They do not support a claim that it prevented a specific percentage more influenza cases than either comparator. Large real-world effectiveness studies would be more informative for determining whether immunogenicity differences translate into fewer infections or severe outcomes across varying influenza seasons.
Such evidence is particularly relevant because circulating influenza strains and vaccine match change every year. A formulation that appears immunologically strong in one antigenic context may produce different relative effectiveness when viral epidemiology shifts.
Post-authorization surveillance could consequently become an important part of the AUJEMFLU evidence package.
What did the Phase 3 study show about tolerability and safety?
The enhanced formulation produced more local and systemic reactions than the comparator vaccines, which is not unexpected for a product combining a higher antigen dose with an adjuvant. Most reactions were mild or moderate and resolved without intervention.
The published dataset did not identify a new safety signal. Serious adverse events through approximately six months occurred in 2.8% of participants receiving the investigational formulation, 3.5% of those receiving the adjuvanted egg-based comparator and 2.9% of participants in the recombinant group.
For seasonal vaccination, tolerability matters because the target population includes millions of generally healthy adults rather than patients accepting substantial toxicity to treat established disease. Even transient injection-site pain, fatigue or systemic symptoms can influence vaccine acceptance when administration occurs annually.
The practical question is therefore whether additional reactogenicity remains modest enough to be acceptable in exchange for stronger immune responses. Regulators in Europe and the United Kingdom have concluded that the benefit-risk profile of the related trivalent formulation supports authorization for adults aged 50 and older.
Ongoing pharmacovigilance will provide a substantially larger safety dataset once use expands beyond clinical trials.
Why is AUJEMFLU trivalent when the published Phase 3 study evaluated a quadrivalent vaccine?
Influenza vaccine composition has been changing because B/Yamagata lineage viruses have not been confirmed in circulation for several years. Global health authorities consequently recommended moving seasonal influenza vaccines from quadrivalent formulations, which included two influenza A strains and two influenza B lineages, toward trivalent products without the B/Yamagata component.
The Phase 3 study was initiated when quadrivalent vaccines remained the relevant development construct. The commercially authorized AUJEMFLU product is trivalent and follows newer strain-composition recommendations.
This means the peer-reviewed quadrivalent study supports the broader platform, formulation and immunogenicity strategy, while the marketed product contains three seasonal strains rather than four.
The distinction is important for accurate regulatory reporting. AUJEMFLU should not simply be described as the exact quadrivalent vaccine studied in the Lancet paper.
The European Commission issued marketing authorization for AUJEMFLU in August 2026 for prophylaxis of influenza in adults aged 50 and older, following a positive regulatory opinion in June. The United Kingdom’s Medicines and Healthcare products Regulatory Agency had already authorized the vaccine in June for the same age threshold.
Commercial introduction will depend on national vaccination recommendations, procurement decisions and access arrangements rather than authorization alone.
Could AUJEMFLU change the competitive landscape for enhanced influenza vaccines?
Older-adult influenza vaccination is already a competitive market containing standard-dose, high-dose, adjuvanted, recombinant and cell-based products. The value proposition therefore cannot simply be that AUJEMFLU is an enhanced vaccine.
Its differentiation lies in combining technologies that competitors frequently use separately. CSL Seqirus can argue that cell-based manufacturing, high antigen content and MF59 adjuvant address different weaknesses in older-adult vaccine responses within one formulation.
The Phase 3 comparison against active enhanced vaccines gives that argument more credibility than a placebo-controlled or standard-dose comparison would provide. Yet the mixed comparison with the recombinant vaccine also prevents an overly simplistic superiority narrative.
National immunization advisory committees will assess far more than antibody titers. Cost, supply reliability, real-world effectiveness, age eligibility, vaccine-program logistics and evidence against severe influenza outcomes can all influence procurement.
CSL Seqirus already has extensive manufacturing and commercial infrastructure in seasonal influenza, potentially giving AUJEMFLU an advantage in distribution and tender participation. The company will nevertheless be competing against well-established products and vaccination policies that vary substantially by country.
What does the new publication mean for CSL Limited investors?
CSL Seqirus is one business within the much larger CSL Limited biotechnology group, meaning the influenza publication is not a binary valuation event comparable with a pivotal result from a single-product biotechnology company. CSL Limited also operates major immunoglobulin, hematology, nephrology and specialty portfolios.
The shares closed at approximately A$171.86 on September 14, gaining roughly 2.9% during the session after closing at A$167.10 on September 11. That move should not be attributed solely to the vaccine publication because CSL trades within a broader Australian market and investors are evaluating group-level earnings, capital allocation and performance across several businesses.
The stock remains below its 52-week high, reflecting a more complicated investor backdrop than the positive vaccine readout alone. AUJEMFLU can contribute to CSL Seqirus’ product renewal and competitive positioning, but commercial materiality will depend on national recommendations, tender wins and uptake across successive influenza seasons.
The Lancet publication nevertheless strengthens the scientific foundation for that effort. CSL Seqirus has shown that combining three enhancement strategies produces stronger immune responses than an established egg-based adjuvanted comparator and generally competitive responses against a higher-dose recombinant vaccine.
The one H3N2 non-inferiority miss is not a trivial footnote, but neither does it negate the overall study. Instead, it provides a useful reminder of how competitive modern influenza vaccine development has become. The commercial question is no longer whether an enhanced vaccine can stimulate immunity, but whether one combination of manufacturing platform, antigen dose and adjuvant can produce sufficiently consistent real-world protection to earn a preferred place in older-adult vaccination programs.